


Telemedicine software cost in 2026 — what you pay to build a telemedicine app or platform — lands in three tiers: $40K–$90K to ship a Tier 1 MVP, $120K–$280K for a Tier 2 EHR-integrated build, and $400K+ at health-system scale. The numbers move because of three forces: how much real-time video you own (P2P vs SFU vs self-hosted media), how deep your EHR integration goes (lightweight EMR vs SMART-on-FHIR launch into Epic / Oracle Health), and how much AI you wire in (ambient scribe, agent-assist, RPM analytics).
Want this scoped for your case? See telemedicine software development.
This is the line-item cost playbook we share with healthcare CTOs and founders before signing an SOW. It separates build cost, run-rate cost and compliance cost, gives realistic 2026 ranges with agent-engineering accelerated delivery, and shows where teams overspend without a corresponding lift in renewal-rate, NPS or claims acceptance. The timing helps: the Consolidated Appropriations Act, 2026 (signed February 3, 2026) extended Medicare telehealth flexibilities through December 31, 2027, so the reimbursement floor under a new build is steadier than it has been since the pandemic.
Key takeaways
• Tier 1 MVP: $40K–$90K, 12–16 weeks. Web + responsive mobile, 1-on-1 video, scheduling, secure messaging, lightweight EMR, e-prescribing, HIPAA controls.
• Tier 2 EHR-integrated: $120K–$280K, 4–6 months. Adds SMART-on-FHIR launch, X12 claims plumbing, AI scribe, multi-state credentialling, role-based dashboards.
• Tier 3 enterprise: $400K+, 9–14 months. Native iOS & Android, multi-tenant white-label, HITRUST CSF, a deep Epic Showroom listing, self-hosted media stack.
• Run-rate matters as much as build cost. A 5K-patient DPC platform runs $1.5K–$5K/month on AWS HIPAA; a 50K-MAU health-system tenant runs $10K–$50K+/month.
• Agent-engineering accelerated delivery shaves 25–40%. Legacy 2022-era estimates ran higher because they assumed manual code-then-review cycles; LLM-assisted scaffolding compresses both code and review.
Updated October 2026: LiveKit Cloud’s new per-participant-minute pricing and HIPAA plan, 2026–2027 regulatory dates (DEA, HHS Section 504, HIPAA Security Rule), off-the-shelf telehealth pricing and current AI-scribe and LLM rates.
Why Fora Soft wrote this telemedicine cost playbook
Fora Soft has been shipping real-time video and audio products since 2005. We’ve shipped 250+ projects with a 50+ person in-house team at a 99% Upwork success score. Telemedicine, healthcare interpretation and HIPAA-compliant video chat are a meaningful share of our 2024–2026 docket. The cost ranges below are not harvested from competitor blogs; they are the ones we actually quote.
Written by Fora Soft’s telemedicine engineering team and reviewed by Polina Sapunova, Fora Soft co-founder and healthcare lead, who has overseen HIPAA-compliant video builds since 2005.
The most directly relevant case is CirrusMED — a HIPAA-compliant DPC ("Netflix for Medicine") subscription telemedicine platform we built from scratch for Preferred Family Medicine, a US private practice. It runs subscriptions from $39/mo for ~1,500 patients, is now licensed across 48+ US states with 20+ physicians on the network, and ships WebRTC video, 24/7 secure messaging, a structured browser-based EMR, and lab/imaging order routing on a React / Node.js / AWS / MongoDB / Twilio / Stripe stack. The owner credited the wireframing & user-story phase for cleaner cost estimation and stack decisions. That is the level of pre-build planning we recommend for every telemedicine app.
For broader context, see our telemedicine development service, our HIPAA-compliant video interpretation platform, the deeper telehealth software guide, and how we wire clinical AI in the LiveKit AI agents guide. Every dollar figure here assumes the controls the HIPAA Security Rule requires — not a "add compliance later" build.
Need a defensible budget for your telemedicine build?
30 minutes, free, no obligation — we’ll review your feature backlog, name a tier, and give you a cost band you can take to the board.
The three cost tiers in 2026 telemedicine builds
Most telemedicine RFPs we see ask the wrong question (“what does it cost to build a telemedicine platform?”) instead of the right one (“which tier am I building, and which features earn back the spend?”). Three tiers cover ~95% of new builds. The bands assume a senior Eastern-European team with agent-engineering delivery; a US agency quotes the same Tier 1 scope at $180K–$320K (see the vendor table below).
| Tier | Build cost (USD) | Calendar time | Best fit | Headline features |
|---|---|---|---|---|
| Tier 1 — MVP | $40K–$90K | 12–16 weeks | DPC, concierge, single specialty | Web + mobile, video, scheduling, EMR, e-Rx, secure messaging, HIPAA |
| Tier 2 — EHR-integrated | $120K–$280K | 4–6 months | Multi-specialty group, Series A startup | + SMART-on-FHIR, claims, AI scribe, multi-state credentialling |
| Tier 3 — Enterprise | $400K+ | 9–14 months | Health system, payer, large IDN spin-out | + Native iOS & Android, multi-tenant white-label, HITRUST, self-host media |
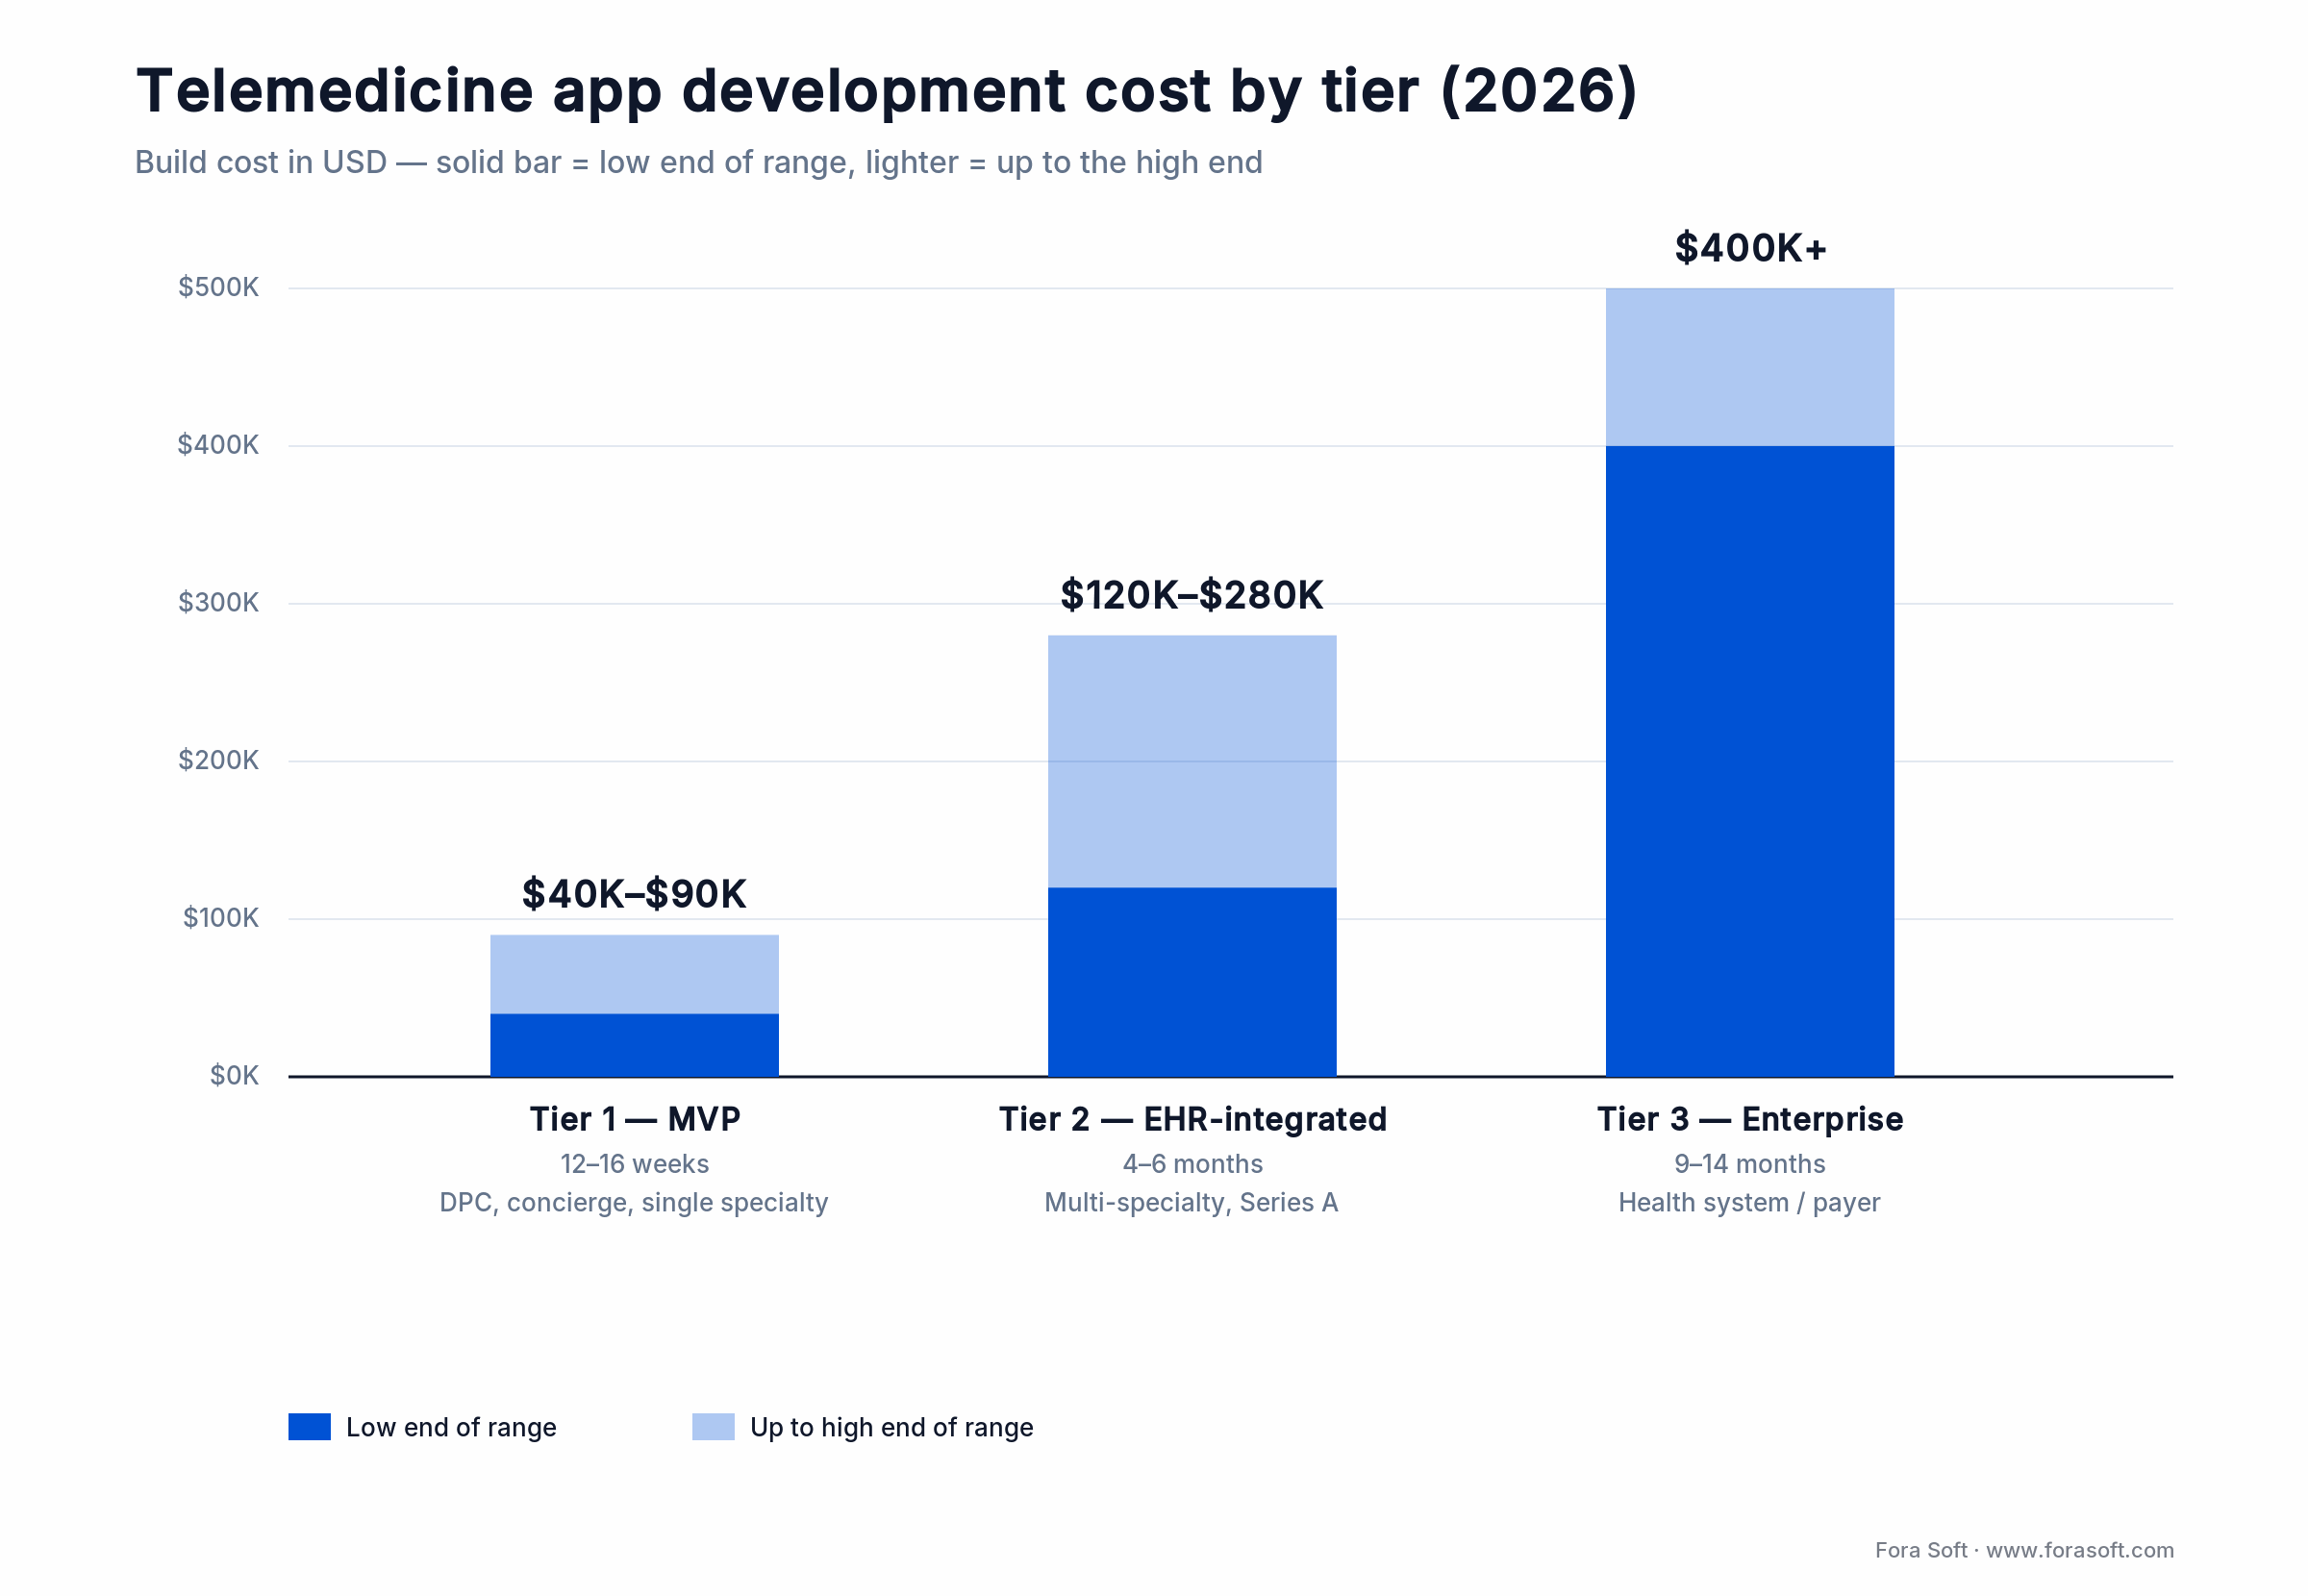
Figure 1. Telemedicine app development cost falls into three tiers — the band shows low-to-high for each.
Reach for Tier 1 when: you have one specialty, one or zero EHR integrations, and a 12–16-week launch window. Most DPC, concierge and behavioral-health builds live here. Don’t pay Tier 2 prices for a Tier 1 problem.
The seven cost factors that actually move the budget
Most cost ranges blow up because of the same handful of decisions. Get these seven right and the budget stays inside the band.

Figure 2. The decisions that swing a telemedicine budget most, ranked by the dollars they add.
1. Video architecture. Peer-to-peer is cheapest and fine for 1-on-1 or a 3–4-person mesh, but it has no server-side recording and still needs paid TURN relays. SFU (LiveKit, Daily, Agora, Chime SDK) is the 2026 default. A self-hosted SFU only earns its keep in the millions of monthly participant-minutes. Wrong call here can add $20K–$80K of media-engineer time.
2. EHR integration depth. A built-in lightweight EMR is the cheapest route ($0 in third-party fees, ~$15K in dev). Aggregators (Redox, 1upHealth) add $10K–$30K in dev plus $1.5K–$8K/month run-rate. Direct SMART-on-FHIR integration with Epic or Oracle Health is $40K–$120K in dev — but the Epic program itself is cheaper than most people quote: Epic Vendor Services runs ~$1,900/year and a Showroom Connection Hub listing ~$500/year (the old "App Orchard" is gone). The cost is the engineering, not the listing fee.
3. AI augmentation depth. Licensing an ambient scribe (Abridge, Suki, DeepScribe, Commure (which absorbed Augmedix in 2024) or Microsoft Dragon Copilot, the 2025 successor to Nuance DAX) runs from about $40–$120 per clinician per month for self-serve scribes (Freed’s published 2026 plans) to an estimated $200–$800+ for enterprise ones such as Abridge and Dragon Copilot, which do not publish prices, plus a 4–6 week integration. Building one costs $40K–$80K in dev and roughly $0.15–$0.35 per visit in STT + token spend — against enterprise licence prices the build crosses over somewhere around 10K–30K monthly visits.
4. Mobile strategy. Browser-only (CirrusMED-style) saves $30K–$60K of native dev. React Native is mid-cost ($40K–$70K). Native iOS + Android adds $80K–$160K. Pick browser-only for v1; add native only when push-notifications, background recording or peripheral integrations (BP cuffs, glucometers) are core to the experience.
5. Compliance scope. HIPAA + BAA chain is table stakes (already in Tier 1). SOC 2 Type II adds $20K–$45K of audit + readiness work, plus $15K–$30K/year in tooling (Vanta, Drata). HITRUST CSF is $80K–$200K and only required by some IDNs.
6. Multi-tenant white-label. Adds $30K–$80K of design-system + admin work in v1. Skipping this and retrofitting later usually costs 2–3× what it would have cost up front; if your roadmap has ≥4 health-system buyers, build multi-tenant from day one.
7. Reimbursement plumbing. Subscription billing (Stripe, Recurly) adds $5K–$15K. Insurance claims (X12 837P + clearing-house, Change Healthcare / Availity / Waystar) adds $25K–$60K plus $1K–$3K/month per clearing-house seat.
Where build dollars actually go — a Tier 1 decomposition
A Tier 1 MVP at the $60K mid-band typically distributes as below. Numbers shift by ±15% depending on team mix and existing assets you bring.
| Workstream | % of budget | $ at $60K mid-band | Notes |
|---|---|---|---|
| Discovery + UX | 12% | ~$7,200 | Wireframes, user-flow maps, FHIR mapping, BAA register |
| Auth + RBAC + audit logs | 10% | ~$6,000 | MFA, 6-yr immutable audit log, RLS multi-tenant |
| Video room (LiveKit/Daily SDK) | 15% | ~$9,000 | Setup + waiting room + recording + bandwidth fallback |
| Scheduling + intake | 10% | ~$6,000 | State-licensure-aware matcher, calendar sync, reminders |
| EMR + e-prescribing | 15% | ~$9,000 | Vitals/allergies/Rx tabs, DrFirst Rcopia integration |
| Messaging + notifications | 8% | ~$4,800 | Sendbird/Stream + Twilio SMS + transactional email |
| Billing (subscription or claims) | 8% | ~$4,800 | Stripe Billing, payment portal, invoice templates |
| DevOps + HIPAA hosting | 10% | ~$6,000 | AWS BAA setup, Terraform, CI/CD, secrets, KMS |
| QA, accessibility, security | 8% | ~$4,800 | WCAG 2.2 audit, pen-test, breach drill |
| PM + buffer | 4% | ~$2,400 | Standups, demos, change-control |
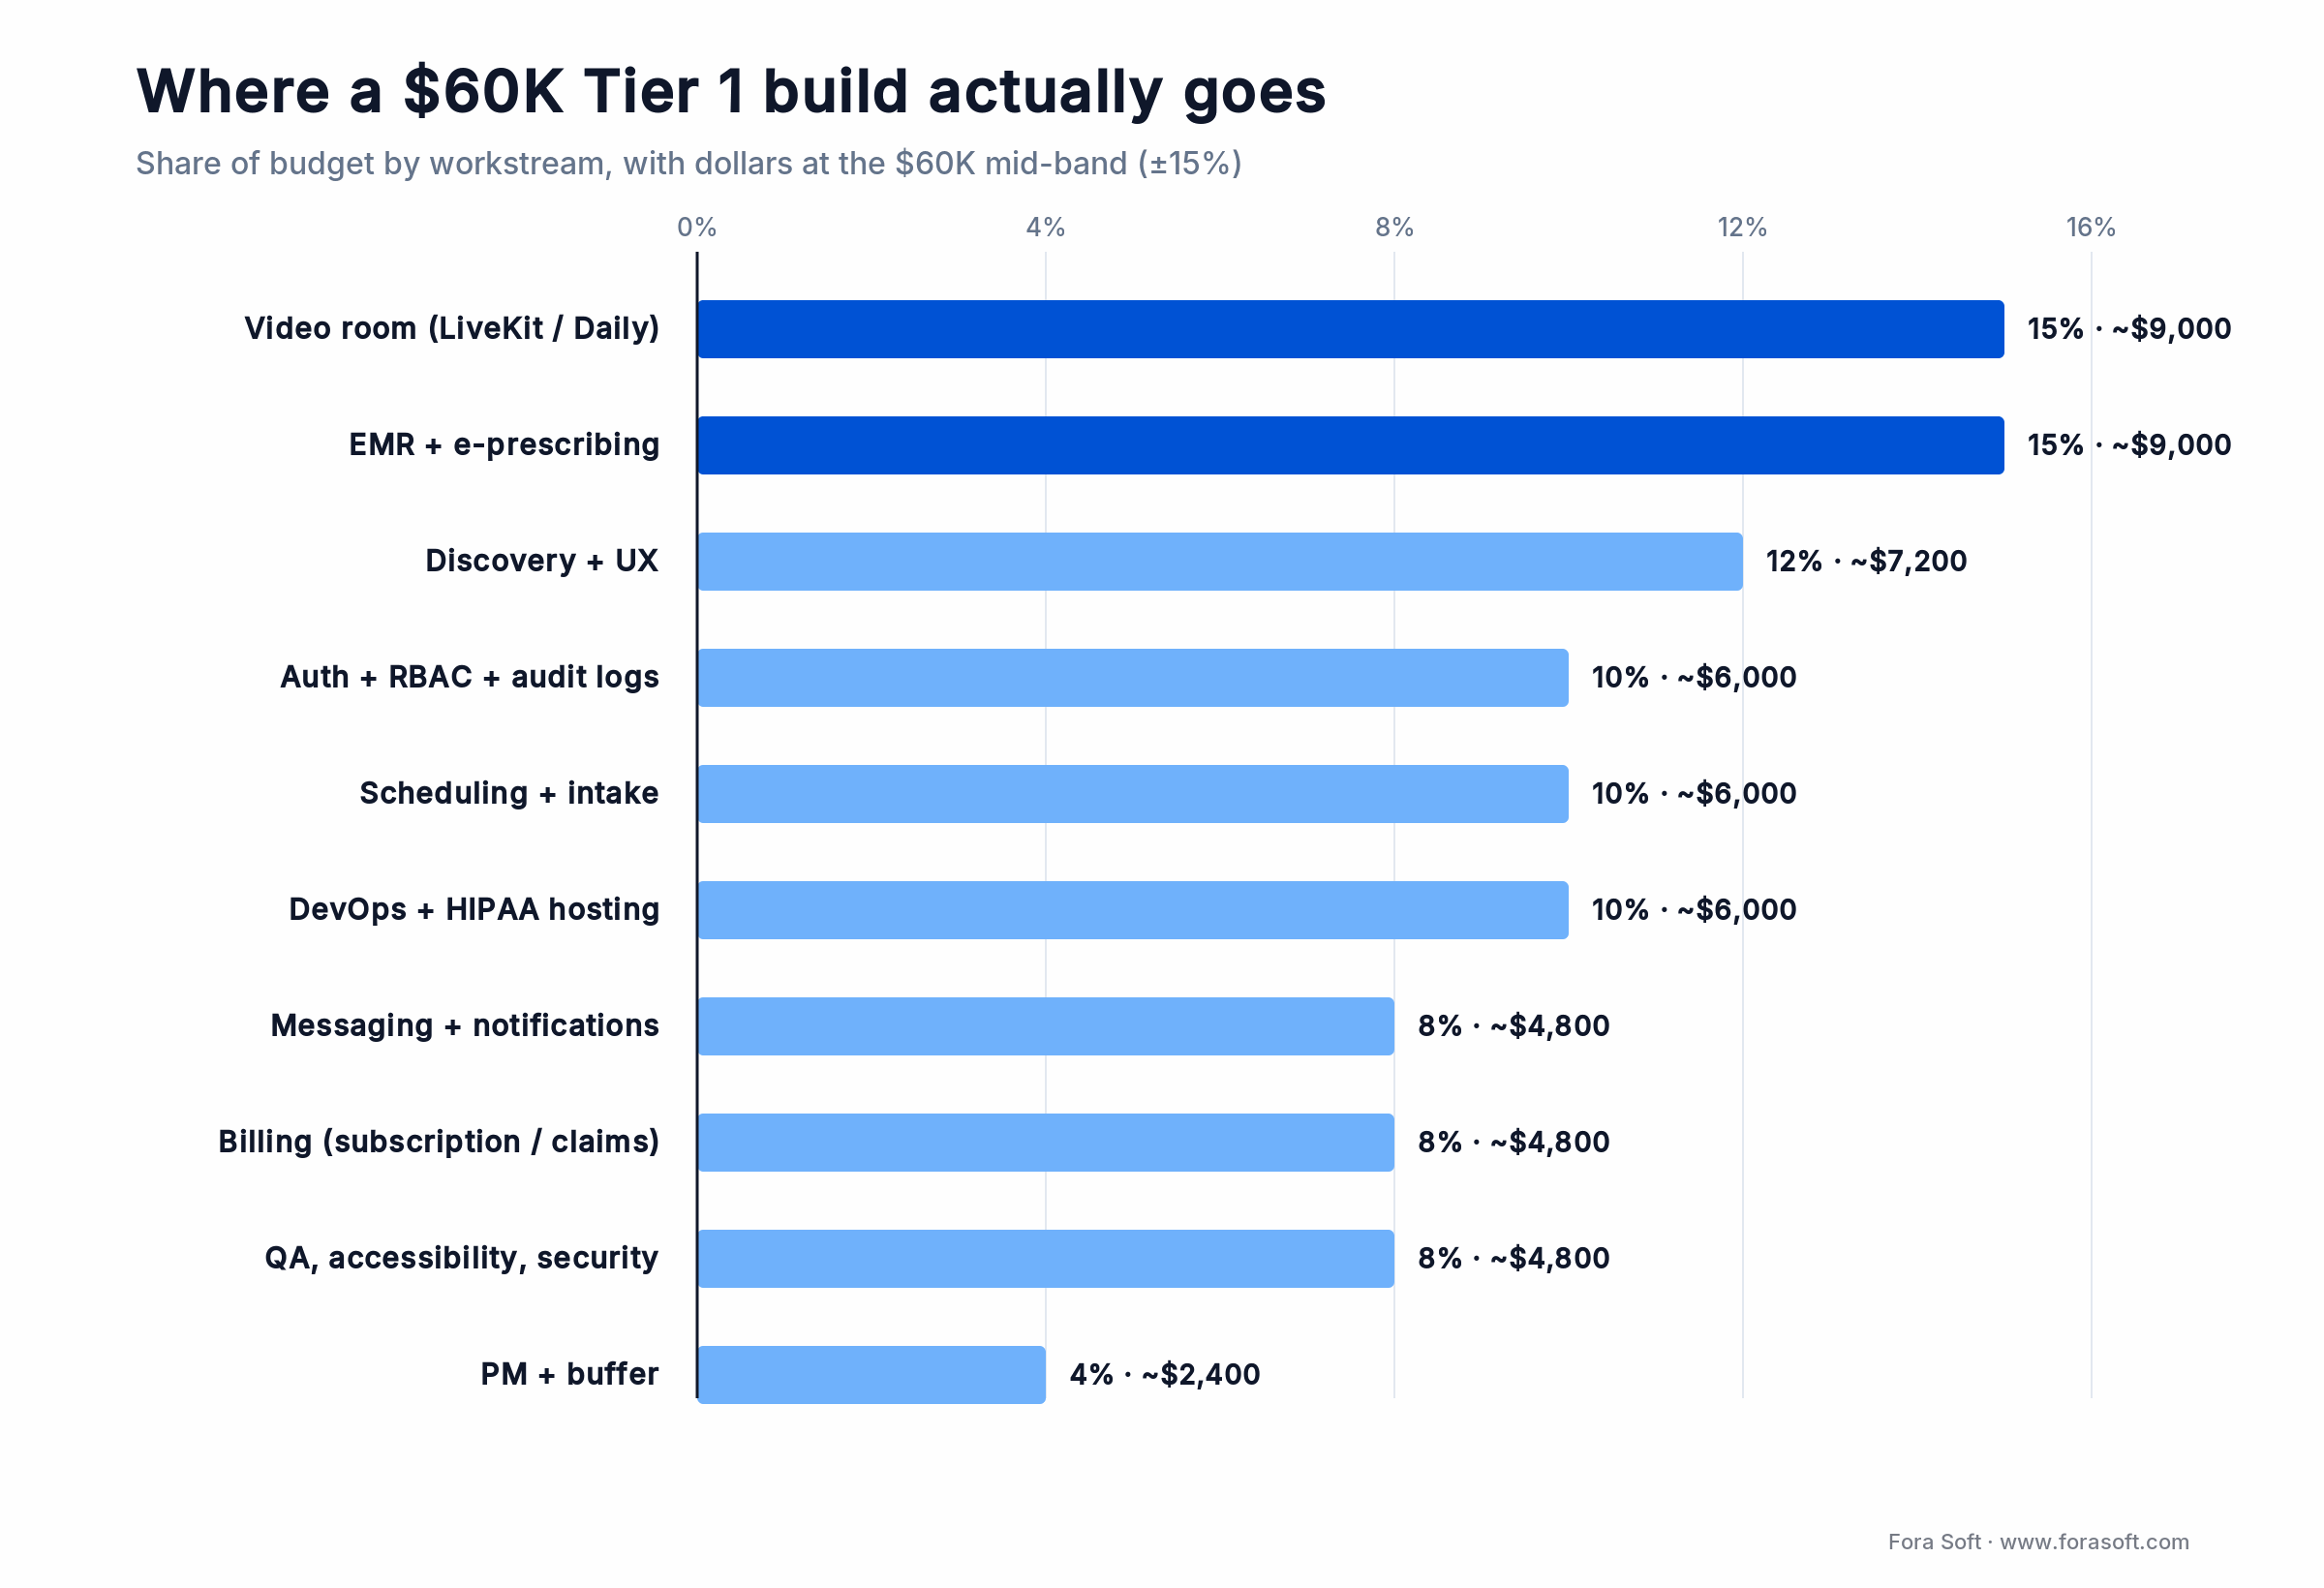
Figure 3. How a $60K Tier 1 build distributes across workstreams (±15% by team mix).
Run-rate — the number that hurts after launch
Build cost is one-off; run-rate eats your runway every month. The shape of run-rate is dominated by hosting + video minutes + AI + clearing-house fees.
1. Cloud hosting (AWS / Azure / GCP under BAA). ~$1.5K–$5K/month for a 1.5K–5K patient DPC platform; $10K–$50K/month at 50K MAU. Dominated by RDS Multi-AZ, EC2 / ECS, S3 storage of recordings, NAT egress.
2. Video minutes. Managed SDKs bill per participant-minute. As of October 2026: Daily charges $0.004/min after 10,000 free minutes, plus $500/month for its HIPAA + BAA add-on; LiveKit Cloud charges $0.0004–$0.0005 per WebRTC participant-minute, but HIPAA is only on its Scale plan (from $500/month, 1.5M participant-minutes included); Agora lists $0.99 per 1,000 audio minutes and $3.99 per 1,000 HD video minutes. A practice running 1,200 visits/month at 25 minutes each ≈ 30,000 minutes × 2 participants = 60,000 participant-minutes ≈ ~$700/month on Daily with HIPAA, or the flat ~$500/month LiveKit Scale plan. The HIPAA plan, not the minutes, is the real floor at clinic scale. Self-hosting only starts to pay in the millions of monthly participant-minutes, and then on BAA-covered compute.
3. AI scribe. Licensed: ~$40–$120 per clinician per month for self-serve tools, an estimated $200–$800+ for enterprise scribes. Built: STT at $0.0043/min pre-recorded or $0.0077/min streaming list price (Deepgram Nova-3; Nova-3 Medical streaming launched at $0.0077/min in 2025) + LLM $0.02–$0.05 per visit (a GPT-5-class model, or Claude Sonnet 5.5 at $2/M input + $10/M output in October 2026, under an Azure OpenAI or Bedrock BAA) + a clinician review UI. Built crosses over enterprise licences around 10K–30K visits/month.
4. Clearing-house. Change Healthcare / Availity / Waystar typically charge $1–$3 per clean claim, with discounts above volume thresholds. A 5K-visit-per-month claims platform sits around $5K–$15K/month.
5. Compliance tooling. Vanta or Drata: $15K–$30K/year for SOC 2 + HIPAA continuous monitoring. Access reviews, vendor BAA register, evidence collection, auditor-friendly export.
6. Observability. Datadog / New Relic / Honeycomb (with BAA) at $1K–$5K/month at MVP scale. Instrument every visit (latency, MOS, ASR WER, LLM token use) before shipping AI features.
Reach for self-hosted LiveKit when: you run several million participant-minutes a month on HIPAA-covered compute and your AI roadmap needs deep media-pipeline control. Below that, LiveKit Cloud’s Scale plan already includes 1.5M participant-minutes for about $500 a month, which no DIY SFU beats once you count SRE on-call time.
Hidden costs that quietly double your budget
The visible build line items are the easy part. These are the ones that show up after the SOW is signed.
1. The full BAA chain. Every PHI-touching vendor (Sentry, Mixpanel, Datadog, AI scribe, transcription) needs a signed BAA — and the legal review for each one runs $500–$2K. Budget $5K–$15K total for the BAA paperwork in a Tier 1 build. The 2024 Change Healthcare ransomware attack, the largest health-data breach in US history at roughly 193 million people (final 2025 count reported to HHS OCR), is the reminder every buyer now brings to the table: one un-vetted vendor in the chain is an enterprise-ending event, not a line item.
2. EHR vendor program fees. Epic replaced App Orchard with Showroom: a Connection Hub listing is ~$500/year and Epic Vendor Services developer membership is ~$1,900/year — far less than the old "App Orchard" pricing people still quote. Oracle Health (Cerner) Code, athenahealth Marketplace and eClinicalWorks run their own programs. An aggregator (Redox, 1upHealth) avoids the per-EHR fee but adds $1.5K–$8K/month for the API.
3. State-by-state credentialling tracking. A platform serving 25 states needs a credentialling-status table, expiry alerts and license-renewal workflow. ~$8K–$20K of dev work, plus ~$300–$700/month per clinician for outsourced credentialling services if you offer that.
4. Pen-tests + security audits. External pen-test before launch: $8K–$25K. Annual SOC 2 Type II audit: $20K–$45K. HITRUST CSF: $80K–$200K. None are optional if you sell to health systems.
5. Accessibility audit (WCAG 2.2). $5K–$15K per major release. HHS’s Section 504 rule requires web and mobile apps of HHS-funded providers to meet WCAG 2.1 AA; a May 2026 interim final rule moved the deadline to May 11, 2027 for recipients with 15+ employees and May 10, 2028 for smaller ones. Build to WCAG 2.2 AA once and you cover that rule and ADA Title III claims.
6. Translation / localisation. Spanish + English are the floor for most US platforms. Each additional language adds $5K–$15K of UI translation and 5–10% to QA. Real-time call translation (AI or human) is its own line item.
7. Insurance. Cyber liability + tech E&O combined typically $15K–$60K/year for a venture-backed startup with PHI and clinical workflows. Rates have hardened post-2023.
The 2026–2027 rule changes that move a telemedicine budget
Five US rule changes decide which features a telemedicine build must carry and how long the reimbursement floor under it holds. None of them adds a new tier; each one changes a line item you would otherwise skip or retrofit later.
| Rule | Status, October 2026 | What it means for the budget |
|---|---|---|
| Medicare telehealth flexibilities | Extended through Dec 31, 2027 by the Consolidated Appropriations Act, 2026; in-person visit for new mental-health patients delayed to Jan 1, 2028; audio-only behavioral telehealth permanent when the patient cannot use video | Home video visits stay billable through 2027; keep an audio-only fallback in the visit room |
| DEA tele-prescribing of controlled substances | Flexibilities extended through Dec 31, 2026; the special-registration rule proposed in January 2025 is not final | Keep EPCS and prescribing rules configurable; reserve a change sprint for whatever applies from 2027 |
| CMS CY 2026 Physician Fee Schedule | Final rule (Nov 2025) makes virtual direct supervision over real-time audio/video permanent and removes frequency limits on subsequent inpatient, nursing-facility and critical-care tele-visits | Supervision and inpatient tele-visit flows are long-term features, not pandemic stopgaps |
| HIPAA Security Rule update | Proposed January 2025 (mandatory MFA, encryption, asset inventory); HHS now targets a final rule in July 2027 | Build MFA, encryption and an asset inventory into Tier 1 now; a retrofit costs more |
| HHS Section 504 accessibility rule | WCAG 2.1 AA for web and mobile; deadline moved to May 11, 2027 (15+ employees) and May 10, 2028 (smaller recipients) | The accessibility audit is a Tier 1 line item, not a nice-to-have |
Hosting cost shape — AWS, Azure, GCP and the alternatives
All three hyperscalers will sign a BAA. The decision usually comes down to existing buyer relationships and which AI services you plan to use.
AWS. The longest list of HIPAA-eligible services and the broadest healthcare ecosystem (Transcribe Medical, Comprehend Medical, HealthLake, Bedrock under BAA). Default for most US telemedicine builds. Tier 1 small platform: $1.5K–$3.5K/month. Tier 3 enterprise: $20K–$80K/month.
Azure. Strong if your buyers are Microsoft-shop hospitals using Epic on Azure. HIPAA-eligible Azure OpenAI is the easiest path to OpenAI’s GPT models under a BAA.
GCP. Best healthcare-data tooling (Cloud Healthcare API for FHIR/HL7v2/DICOM, Healthcare Natural Language). Stronger choice if FHIR ingestion + analytics is a v1 feature.
Specialty HIPAA-managed. ClearDATA, Aptible, Atlantic.Net offer white-glove HIPAA hosting with deeper compliance hand-holding at a 30–60% premium over hyperscaler list prices. Useful if you don’t have an SRE on staff.
Hetzner / bare-metal. Cheaper bandwidth, but these hosts do not sign a BAA, and an SFU decrypts media to forward it, so PHI passes through the box. Keep clinical video on BAA-covered compute; bare metal fits only non-PHI workloads such as marketing streams or synthetic load tests.
In-house vs offshore vs nearshore vs partner — the real cost gap
Vendor location is the loudest factor in legacy cost-comparison blogs. The picture in 2026 is more nuanced because agent-engineering accelerated delivery has flattened velocity differences across regions, while compliance stays geography-dependent.
| Vendor type | Effective hourly rate (2026) | Tier 1 MVP cost | Trade-offs |
|---|---|---|---|
| US in-house team | $120–$200 | $140K–$260K | Full ownership, hardest to scale up/down |
| US agency | $150–$280 | $180K–$320K | Healthcare familiarity, premium pricing |
| Nearshore (LATAM) | $60–$110 | $80K–$160K | Time-zone friendly, healthcare experience varies |
| Eastern Europe | $45–$85 | $45K–$110K | Strong WebRTC bench, deep video expertise |
| South / Southeast Asia | $25–$60 | $25K–$80K | Cheapest, hardest on healthcare-specific QA |
Reach for an Eastern-Europe partner with healthcare experience when: you want healthcare-grade QA, deep WebRTC expertise, and 50–65% cost savings vs a US agency — without giving up time-zone overlap. This is where Fora Soft sits: our AI telehealth video platform development covers HIPAA-ready WebRTC video and EHR integration over FHIR R4.
Want a cost-band you can take to the board?
Send us a one-paragraph brief — we’ll come back with wireframes, a stack recommendation, a cost band, and a 12–16-week milestone plan, free.
Third-party SDK and tooling prices that quietly drive telemedicine app development cost
A surprising share of telemedicine app development cost lives in the third-party SDK contracts you sign in week three of the build. The list below is the 2026 pricing snapshot we use in scoping calls.
Video SDK. LiveKit Cloud ($0.0004–$0.0005 per participant-minute, HIPAA on the $500/month Scale plan) and Daily ($0.004 per participant-minute, $500/month HIPAA add-on) anchor the low end in October 2026; Agora lists $0.99 per 1,000 audio and $3.99 per 1,000 HD video minutes; Twilio Video is still an option (Twilio reversed its 2024 shutdown plan and keeps it supported), as is the Amazon Chime SDK (unaffected by the retirement of the consumer Amazon Chime app). Volume discounts start above ~1M minutes/month. We break these numbers down in our LiveKit vs Agora cost analysis.
STT for ambient scribe. Deepgram Nova-3 at $0.0043/min pre-recorded and $0.0077/min streaming list (Nova-3 Medical streaming launched at $0.0077/min); AssemblyAI at ~$0.006/min pre-recorded and ~$0.010/min streaming with its $0.15/hour Medical Mode add-on; Azure Speech (HIPAA) at ~$0.017/min. Prices as of October 2026; streaming promos come and go, so budget on list price.
LLM for SOAP-note generation. A GPT-5-class model on Azure OpenAI (BAA) or Claude Sonnet 5.5 on Bedrock (BAA; $2/M input + $10/M output on Anthropic’s October 2026 price list) both work. A typical 25-minute visit consumes 5K–9K input tokens plus a 1K–2K-token note → roughly $0.02–$0.05 per visit, more with multi-pass review prompts.
Messaging. Sendbird HIPAA tier from ~$1K/month; Stream Chat enterprise from ~$1.5K/month; Twilio Conversations + SMS at usage prices.
e-Prescribing. DrFirst Rcopia and Surescripts both quote per-provider per-month, typically $40–$90 base + EPCS module. Implementation fees $5K–$15K.
Clearing-house. Change Healthcare, Availity, Waystar at $1–$3 per clean claim with discounts at volume; eligibility checks at $0.05–$0.15 per inquiry.
Reach for managed Cloud SDKs first when: you have under a few million monthly participant-minutes — no DIY SFU pays back below that once you account for SRE on-call burden and the security compliance work a self-hosted media stack pulls in.
How competing vendors price telemedicine builds — the 2026 reality
Buyers comparing quotes side-by-side often see 3–4× spreads on the same scope. Here is what is actually behind those spreads.
1. Discovery depth. Vendors who quote on a one-call SOW, no wireframes, are not pricing the same product. Premium quotes include 1–2 weeks of paid discovery; the spread evaporates once both vendors have read the same threat model and FHIR mapping.
2. Senior-vs-junior mix. A $45/hr quote that is 80% junior + 20% mid is not the same as a $90/hr quote that is 30% senior + 50% mid + 20% junior. The senior mix typically delivers 2–3× faster on the hard parts (media, FHIR, security).
3. Healthcare-specific overhead. A vendor who has shipped HIPAA platforms before has reusable BAA templates, threat-model libraries, audit-log scaffolds and SOC 2 evidence-collection patterns. That overhead is real and should be priced in — vendors who skip it usually rediscover it in production.
4. AI-assisted delivery. Agent-engineering accelerated teams (LLM-assisted code, review and test scaffolding) typically deliver 25–40% faster on the same scope. That speed-up should show up in the quote, not get pocketed as margin.
5. Buffer transparency. A 15–20% project-management + change-control buffer is reasonable; a 35–45% “contingency” is the vendor pricing the discovery they did not do. Ask for the line items.
Mini case — CirrusMED, the cost frame for a DPC telemedicine platform
Situation. Preferred Family Medicine, a US private practice, wanted to escape per-visit billing and run a DPC subscription model: monthly / quarterly / annual plans starting at $39/mo with unlimited video visits, 24/7 secure messaging, lab orders, prescriptions and a lightweight EMR — all HIPAA-compliant, all in-browser, no app download.
Build shape. A Tier 1 MVP plus a small set of v1.1 features: WebRTC video chat, doctor-availability scheduling with SMS & email reminders, 24/7 doctor-patient messaging, structured EMR (vitals, allergies, family history, surgeries, social history, prescriptions, BMI auto-calc), lab/imaging order routing direct to testing centers, subscription billing for DPC plans. Full case study at forasoft.com/projects/cirrusmed.
Outcome. All ~1,500 patients in the founding practice now video-chat with their physicians on the platform, which today runs a DPC subscription network of 20+ physicians licensed across 48+ US states and keeps expanding online-first. The owner credited the wireframing and user-story phase, one of the cheapest deliverables in the build, for cleaner cost estimation and stack decisions.
“A detailed wireframing and user stories are done in a fantastic way and timely fashion. All my requirements are taken care of. Highly recommended!” Christopher Highley, Owner, Preferred Family Medicine
ROI math — when telemedicine software actually pays back
A telemedicine build pays back the day a clinician’s panel grows by 8–12% without proportional payroll growth, or the day a DPC subscription cohort breaks even on customer-acquisition cost.
1. Clinician throughput. Ambient AI scribing returns 1–2 hours/day to a clinician. At 5 patients/hour and a $200 average reimbursement, that is $1,000–$2,000 of additional daily capacity per clinician — roughly $25K/month at full utilisation. A 10-clinician group recovers a $90K Tier 1 MVP in ~5 weeks, even at a partial utilisation ramp, if the scribe is the headline feature.
2. No-show reduction. In-person no-show rates run ~25%; telehealth cuts that to roughly 12% (2024–2025 peer-reviewed studies, including a 2025 BMC Health Services Research meta-analysis), and automated reminders push it lower still. Each recovered visit at $200 reimbursement is close to pure margin. A 1,000-visit/month clinic that shaves 13 percentage points off its no-show rate recovers ~$26K/month, and a 2025 Tebra survey put the average practice’s no-show losses near $22,900/year, so a good scheduling module pays for itself fast.
3. Claims clean-rate. Going from a 90% to a 98% claims clean-rate at $200 average reimbursement on 5K monthly visits is ~$80K/month of cash collected without payer call-back.
4. DPC subscription LTV. A $39/mo DPC subscription has ~$700–$1,200 LTV at 18–30 month average tenure. Customer-acquisition cost typically lands $80–$200 in healthcare DTC. The LTV/CAC math is friendlier than most other consumer SaaS verticals.
A decision framework — pick your tier in five questions
Q1. How many clinicians and patients are on the platform in year one? <10 clinicians + <5K patients = Tier 1. 10–50 clinicians + up to 50K patients = Tier 2. 50+ clinicians + multi-tenant = Tier 3.
Q2. Do you need direct integration with Epic, Oracle Health, Athenahealth or eClinicalWorks? If yes — Tier 2 floor; aggregator (Redox, 1upHealth) keeps you below Tier 3 unless you have >20 customer sites of the same EHR.
Q3. Are you billing insurance, subscriptions, or both? Insurance only = Tier 2 (claims plumbing). Subscriptions only = Tier 1 fits. Both = Tier 2.
Q4. Do clinicians want native mobile, or is browser-only OK? Browser-only saves $30K–$60K. Native iOS + Android adds $80K–$160K. Default to browser-only unless peripheral integrations or background recording are core.
Q5. Are you selling to health systems? Yes — SOC 2 Type II is mandatory; HITRUST may be. Add $35K–$200K in compliance overhead. No — you can stop at HIPAA + a security questionnaire library.
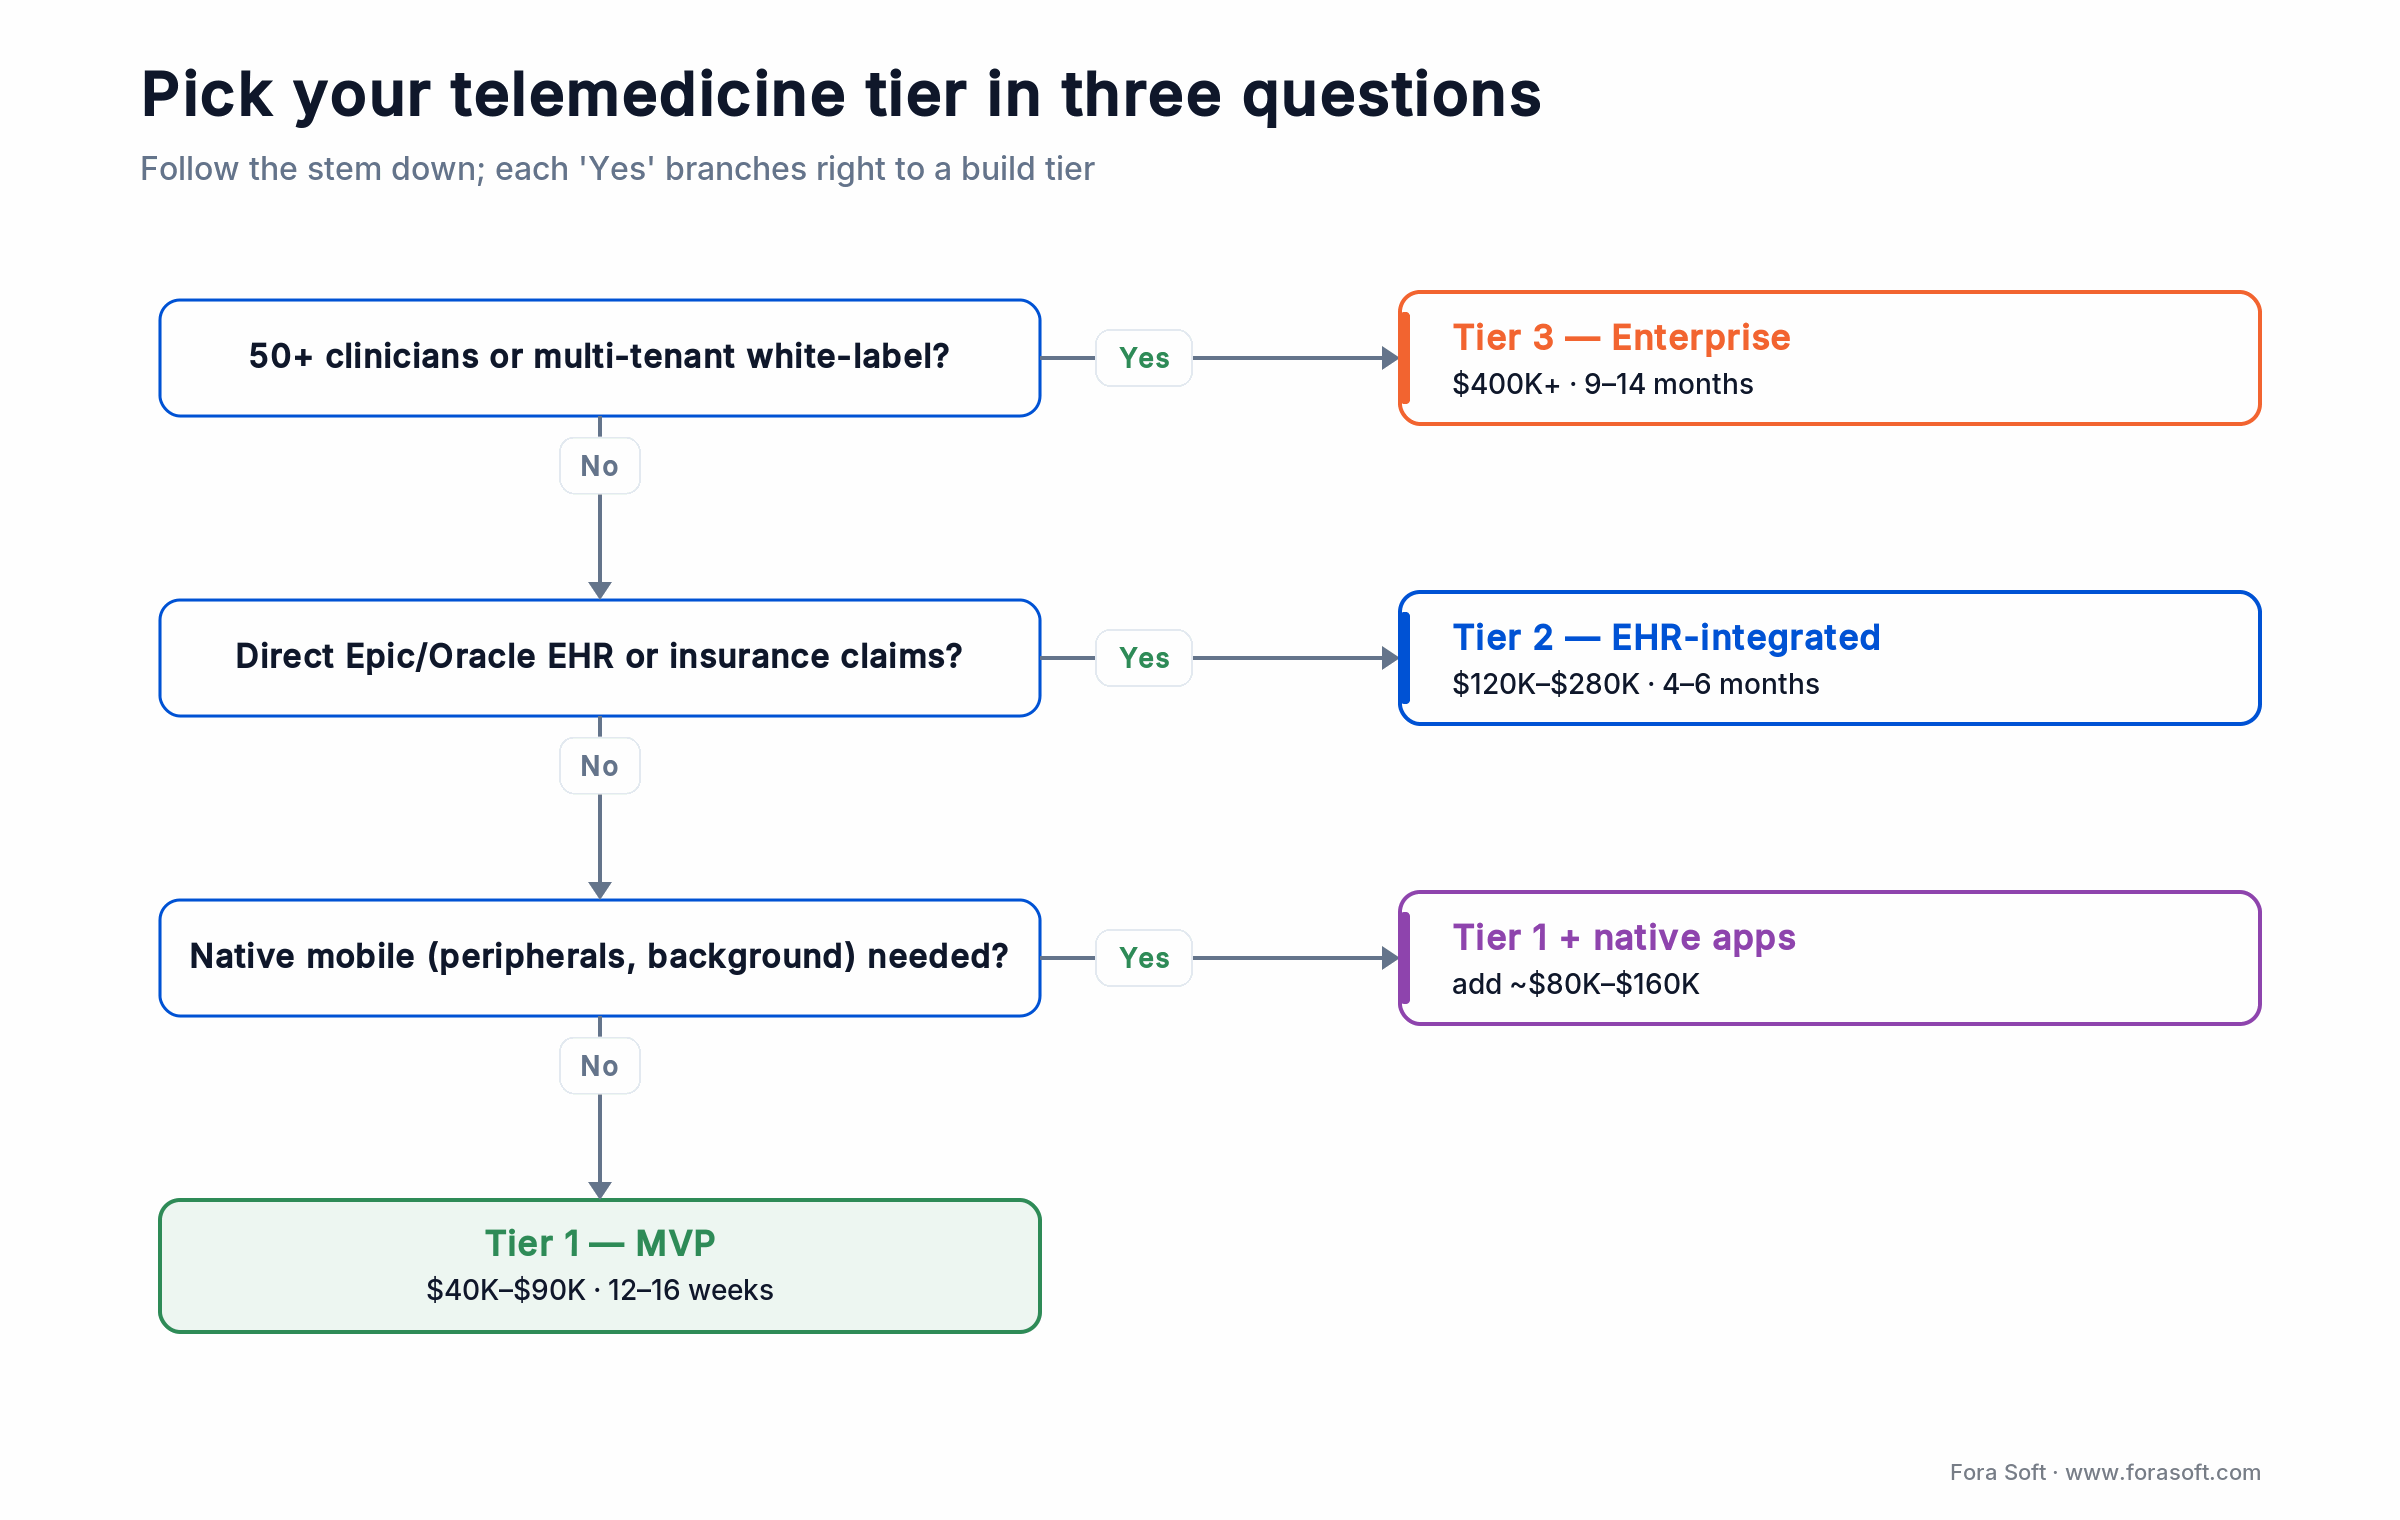
Figure 4. Three questions route most builds to the right tier before you ever price a feature list.
Five cost pitfalls we keep cleaning up
1. Building a custom SFU when LiveKit Cloud or Daily would do. $30K–$80K of media-engineer time spent reproducing SDK features that LiveKit Cloud sells for under $0.001 per participant-minute (plus its $500/month HIPAA plan). Self-host once concurrency justifies it — not before.
2. Buying a generic chat platform without a BAA. The cheapest chat SDK without a BAA is the most expensive choice once OCR notices it. Always Sendbird/Stream/Twilio at HIPAA tier — $1K–$3K/month is a small price.
3. Over-investing in v2 features pre-launch. Emotion detection, AR, and metaverse demos eat $30K–$80K and rarely move renewal-rate. Ship the floor; iterate after first cohort.
4. Skipping discovery to “save” $5K–$10K. Discovery is 10–15% of total spend and it is the line item with the highest payoff. Skipping it tends to add $20K–$60K of rework downstream. Our MVP planning sprint produces exactly these artifacts: feature priorities, wireframes and a cost band per phase.
5. Picking the cheapest offshore vendor for compliance work. HIPAA control implementation requires US legal-context literacy. The savings on dev rates are typically eaten by the security audit findings later. Mix-and-match: senior healthcare-experienced architects for compliance + offshore for build velocity.
KPIs — tying the spend to outcomes
Quality KPIs. Visit completion rate ≥90%, MOS audio ≥4.0 (1–5), glass-to-glass latency ≤300ms p95, ASR word-error-rate ≤8% on medical terms, clinician-edited AI scribe sentences ≤15%. These are the technical floor that protects build ROI.
Business KPIs. No-show rate <5%, time-to-first-visit, NPS ≥45, claims clean-rate ≥98%, net collection rate 95–99%, 90-day & 12-month patient retention. These are what your investors and your CFO ask about.
Reliability KPIs. 99.95% uptime on the visit room, <1% disconnects per visit, mean-time-to-recover <15 min for media outages, audit-log integrity 100% (zero gaps in retention), <60-second cold-start on clinician dashboard.
Telehealth software pricing if you buy instead of build
Off-the-shelf telehealth software costs roughly $0–$120 per clinician per month in 2026, against $40K+ to build your own. Practice-management suites with telehealth, such as SimplePractice, list $49, $79 and $99 monthly solo plans (group Plus: $99 for the first clinician and $74 for each additional one, October 2026). Doxy.me has a free tier and a paid Premium plan that includes a BAA. Most EHRs, including Epic, Oracle Health and athenahealth, ship a built-in video module.
The math favors buying until the platform itself is the product. A 10-clinician group on SimplePractice’s group Plus plan ($99 + 9 × $74) pays about $9K a year; a $60K Tier 1 build plus $18K–$60K a year of run-rate only wins when you sell the care model itself (DPC subscriptions, a multi-state virtual clinic, a white-label for health systems) or when per-seat fees scale past a few dozen clinicians. For a custom platform we also budget 15–20% of the build cost per year for maintenance and dependency updates.
When NOT to spend the money on a custom build
Custom telemedicine is the wrong spend in at least four situations. If any of these is you, license an off-the-shelf tool and grow into a custom build later.
Single physician, <100 visits/month. Doxy.me, SimplePractice or your existing EHR’s built-in video module is fine.
You don’t have a unique workflow. If your edge is “like Doxy.me but for our brand,” that is a marketing problem, not a software problem.
Runway under 12 months. Custom telemedicine has a long compliance tail. License-and-grow until you can fund a year of ops on top of build.
Single existing health system that loves its EHR. Use Epic Telehealth or Oracle Health’s native video, integrate around the edges, ship in 6 weeks.
Stuck between Tier 1 and Tier 2 budgets?
Tell us your patient volume, payer mix and EHR — we’ll tell you which tier you actually need, and where the numbers will move based on your roadmap. Honest answer, even if it’s not us.
Roadmap-to-budget — how a 16-week sprint plan ties to invoices
A clean budget mirrors a clean phase plan. Below is how a $60K Tier 1 build distributes across the 16-week schedule we use.
| Weeks | Phase | Cost (mid-band) | Output |
|---|---|---|---|
| 1–2 | Discovery | ~$8K | Wireframes, BAA register, FHIR mapping, threat model |
| 3–4 | Foundations | ~$8K | Auth, RBAC, multi-tenant skeleton, audit-log spine, CI/CD |
| 5–7 | Visit room | ~$11K | LiveKit/Daily integration, scheduling, intake, in-call chat |
| 8–10 | Clinical workflow | ~$12K | EMR or FHIR adapter, e-Rx, lab orders, secure messaging |
| 11–12 | AI augmentation (optional) | ~$8K | Ambient scribe pipeline, real-time captions |
| 13–14 | Billing & ops | ~$7K | Subscriptions or X12 837P generator, reporting |
| 15–16 | Pre-launch | ~$6K | Pen-test, breach drill, WCAG 2.2 audit, pilot launch |
FAQ
What is the cheapest realistic Tier 1 telemedicine build in 2026?
$40K–$50K with an Eastern-Europe partner using agent-engineering accelerated delivery on a managed video SDK (LiveKit Cloud or Daily) plus a built-in lightweight EMR. Below that band, you are buying a demo, not a HIPAA-survivable production product.
How much does a telemedicine platform cost to run per month?
A 1.5K–5K patient DPC platform runs $1.5K–$5K/month on AWS HIPAA. A 50K MAU health-system tenant runs $10K–$50K+/month, dominated by RDS Multi-AZ, video minutes (LiveKit Cloud / Daily), recording storage, and clearing-house fees. Self-hosting LiveKit on BAA-covered compute only becomes cheaper in the millions of monthly participant-minutes.
Should I license an AI scribe or build one?
License (Abridge, Suki, DeepScribe, Commure or Microsoft Dragon Copilot) while you are under roughly 10K–30K monthly visits — faster to ship, no training overhead, KLAS-rated quality. Build above that range when token + STT economics flip in your favor and you want to own the prompt-engineering loop. Most platforms license in v1 and revisit later.
Why do legacy estimates run higher than 2026 ones?
Two reasons. First, agent-engineering accelerated delivery has compressed the code-review cycle by 25–40%. Second, the SDK ecosystem has matured — in 2022 a custom SFU was a real option; in 2026, LiveKit Cloud and Daily are mature enough that build-vs-buy bends towards buy for nearly every Tier 1 and Tier 2 build.
How much does HIPAA + SOC 2 readiness add to the budget?
HIPAA controls are baked into Tier 1 (audit logs, BAAs, encryption, RBAC, MFA). SOC 2 Type II adds $20K–$45K of audit + readiness work plus $15K–$30K/year in tooling (Vanta, Drata). HITRUST CSF is a step further at $80K–$200K and only required by some IDNs.
How long until a custom telemedicine platform pays back?
For a multi-clinician group, a Tier 1 MVP with ambient AI scribing typically pays back in 5–12 weeks of clinical operation through clinician throughput gains alone. For a DPC startup, payback depends on subscriber acquisition; LTV/CAC is usually friendlier than other consumer SaaS verticals.
Do clearing-houses or claims integrations add a lot of cost?
$25K–$60K of dev to wire up X12 837P generation, eligibility checks (270/271), ERA ingestion (835), plus $1–$3 per clean claim through Change Healthcare, Availity or Waystar. Necessary if you bill insurance; skip entirely if you are subscription-only DPC.
How much should a small clinic network budget for an iOS/Android telehealth app connected to Epic via FHIR?
Plan for Tier 2: $120K–$280K and 4–6 months for mobile apps with a SMART-on-FHIR launch into Epic, plus about $1,900 a year for Epic Vendor Services and roughly $4K–$12K a month of run-rate once hosting, the HIPAA video plan, chat, observability and any FHIR aggregator are counted. React Native keeps you in the lower half of the band; fully native iOS and Android adds $80K–$160K.
What is a reasonable timeline and budget for a telehealth MVP with EHR integration?
A Tier 1 MVP with a built-in EMR takes 12–16 weeks and $40K–$90K. Replacing the built-in EMR with a real EHR integration adds $10K–$30K through an aggregator such as Redox, or $40K–$120K for direct SMART-on-FHIR with Epic or Oracle Health, and stretches the plan to 4–6 months.
Is a white-label telehealth kit cheaper than building everything in-house?
A white-label kit gets a branded video-visit app live in weeks for a subscription, but you rent its roadmap and pay per seat or per minute for as long as you run it. Building on managed SDKs such as LiveKit or Daily costs $40K–$90K for Tier 1 and you own the workflow; making your own platform multi-tenant white-label adds $30K–$80K.
How much does a simple video visit app with scheduling, secure chat and payments cost?
About $40K–$60K, the low end of Tier 1, with a managed video SDK, a HIPAA-tier chat SDK and a card-payments integration. Run-rate starts around $3K–$6K a month, because the HIPAA video plan (about $500 a month on LiveKit Scale or Daily), the HIPAA chat tier ($1K+), hosting and observability are fixed costs regardless of volume.
How does Fora Soft price a telemedicine platform build?
Fixed-band on the discovery sprint (1–2 weeks), then fixed-band per phase or T&M with a hard cap. We share an honest cost band on the first call — if it’s Tier 1, we say so. Agent-engineering accelerated delivery typically lands at the lower end of the ranges in this article.
What to read next
Architecture
Telehealth Software Guide: AI, HIPAA, Build Cost
The full 2026 stack for AI-powered video consultations — SDK choice, FHIR, AI scribe, hosting.
Feature set
Telemedicine Features 2026: Must-Have Floor & AI
Which features absolutely have to ship in v1, which are v1.1, and which can wait.
Video stack
P2P vs MCU vs SFU: Which to Pick
When peer-to-peer breaks, when SFU wins, when MCU still earns its keep on real-time video.
AI agents
LiveKit AI Agent Development
How we wire ambient scribes and clinical agents into LiveKit-based telemedicine visits.
Ready to size your telemedicine platform development cost properly?
A defensible telemedicine platform development cost in 2026 follows a tier shape: $40K–$90K Tier 1, $120K–$280K Tier 2, $400K+ Tier 3. The number that matters is not the headline build but the all-in spend across build + run-rate + compliance + clearing-house + observability for the first 12 months. Get the tier right, license the SDK and AI features that make sense, and the platform pays back inside the first half-year.
If you are between tiers, the cheapest dollar you spend is on a 30-minute scoping call with someone who has shipped this shape of platform before. We will tell you the tier, the line items that move, and the ones you can skip safely.



The handbook · 7 volumes
Fora Soft Video Engineering Handbook
Behind every cost tier in this guide is a video layer that has to hold up in a real consult, under HIPAA and on a patient's weak home network. We wrote a seven-volume handbook on the full video stack, from encoding and delivery to sound and AI. Start with the volume on WebRTC, players and QoE, then the AI volume on live captions and regulation, and Video Encoding for bandwidth. Written by Nikolay Sapunov, CEO at Fora Soft.
Browse the handbook on Amazon →7 volumes · 9,000+ pages · Kindle & paperback
Let’s pressure-test your telemedicine budget
Free 30 minutes — we’ll review your feature backlog, name the tier, point out the line items that hurt, and give you a cost band you can take to the board.

