

Key takeaways
• Custom AI medical imaging software wins on workflow, not model accuracy. A 0.92 AUC model that lives inside PACS and updates the worklist in 30 seconds beats a 0.96 model sitting in a separate viewer, and we have yet to see an exception.
• The regulatory path drives 40–60% of timeline and cost. FDA 510(k) adds 9–15 months and $150K to $400K on top of engineering. CE marking under EU MDR adds 6–12 months and €100K to €300K. Plan for it from week one.
• Realistic build ranges with Agent Engineering. PoC on retrospective data in 6–10 weeks: $30K to $80K. Production MVP integrated with PACS/RIS: $120K to $260K. Cleared class-II device with deployment and monitoring: $320K to $750K, delivered 25–35% faster than traditional agency benchmarks.
• The dataset is the product. Public sets (NIH ChestX-ray14, LIDC-IDRI, MIMIC-CXR, The Cancer Imaging Archive) will carry a PoC. Clinical-grade performance needs 10K–100K de-identified studies from 3+ sites and a written annotation protocol.
• Market is real and growing about 27% a year. Precedence Research (2026 edition) puts AI in medical imaging at $2.57B in 2026 and $22.97B by 2035. The FDA’s September 2026 list update counts 1,614 AI-enabled devices, 76.2% of them in radiology. The leaders are specialists: Aidoc in triage, Viz.ai in stroke, Rad AI in reporting, Paige in pathology. Each owns a narrow use case and fits deep into one workflow.
Updated November 2026: FDA AI-enabled device list at 1,614 (September 2026 update, 76.2% radiology); Aidoc’s January 2026 510(k) for foundation-model CT triage; HIPAA Security Rule final action now projected for July 2027; CY 2027 Medicare fee schedule cut.
Why Fora Soft wrote this playbook
We’ve built video, AI, and healthcare software since 2005: 250+ delivered projects and a 99% Upwork success rate. Medical imaging AI combines three things we ship all the time: computer vision and deep learning, video and imaging pipelines, and healthcare integrations with heavy compliance requirements. See our AI integration services, telemedicine platform work, and the page of our medical imaging software development team for the full picture.
This playbook comes from patterns that made it to production. Our real-time AI emotion analysis work runs CNNs on live video at clinical latency. The AI video quality enhancement pipeline uses the same class of model you would use to upscale low-dose CT. BrainCert serves 100,000+ users across 10 regional data centers with HIPAA-adjacent security controls, so we know how to build infrastructure that passes regulated-industry audits. VALT, the HIPAA video-surveillance platform where we have been the sole development team for 10+ years, runs the same security posture in production for 770+ US organizations and 50,000+ users.
We deliver with Agent Engineering: specialist agents work in parallel on the data pipeline, model training, PACS integration, compliance, QA, and frontend. As a result, AI medical imaging software MVPs typically ship 25–35% faster and cheaper than a traditional agency quote. Every cost, timeline, and trade-off below assumes that delivery model.
Scoping a medical imaging AI product?
30 minutes with our ML and regulatory architects. We’ll sketch use case, dataset strategy, PACS integration, and a realistic clearance-aware timeline — no sales deck.
What “custom AI for medical imaging” actually means
AI medical imaging software is software that reads medical images (CT, MRI, X-ray, ultrasound, mammography, whole-slide pathology) and returns a finding, a measurement, a triage score or a draft report inside the clinician’s existing workflow. Custom medical image analysis software does the same job but is built for one indication, one dataset and one buyer rather than licensed off the shelf. In the US it becomes a regulated medical device once it analyzes an image to inform a clinical decision.
Medical imaging AI comes in four deployment patterns. Picking the right one matters more than gaining 2 points of F1.
1. Worklist triage. The model reads every study as it arrives in PACS, scores it for urgency (intracranial hemorrhage, pulmonary embolism, large-vessel occlusion), and moves urgent cases to the top of the radiologist’s list. Aidoc and Viz.ai built their businesses on this pattern. Success metric: time to notification.
2. Detection and measurement assist. The model marks candidate findings (lung nodules, fractures, lesions) on the study, and the radiologist accepts or rejects them in the reporting workflow. Success metric: sensitivity at an acceptable false-positive rate per study.
3. Quantification and follow-up. The model segments organs or lesions, measures volumes, and tracks change against prior studies: RECIST 1.1 in oncology, left-ventricular ejection fraction in cardiology. Success metric: agreement with expert ground truth.
4. Reporting and orchestration. An LLM drafts the radiology report from pixel-level findings plus clinical context. Rad AI leads this category. Success metric: time saved per study and edit distance between the draft and the final report.
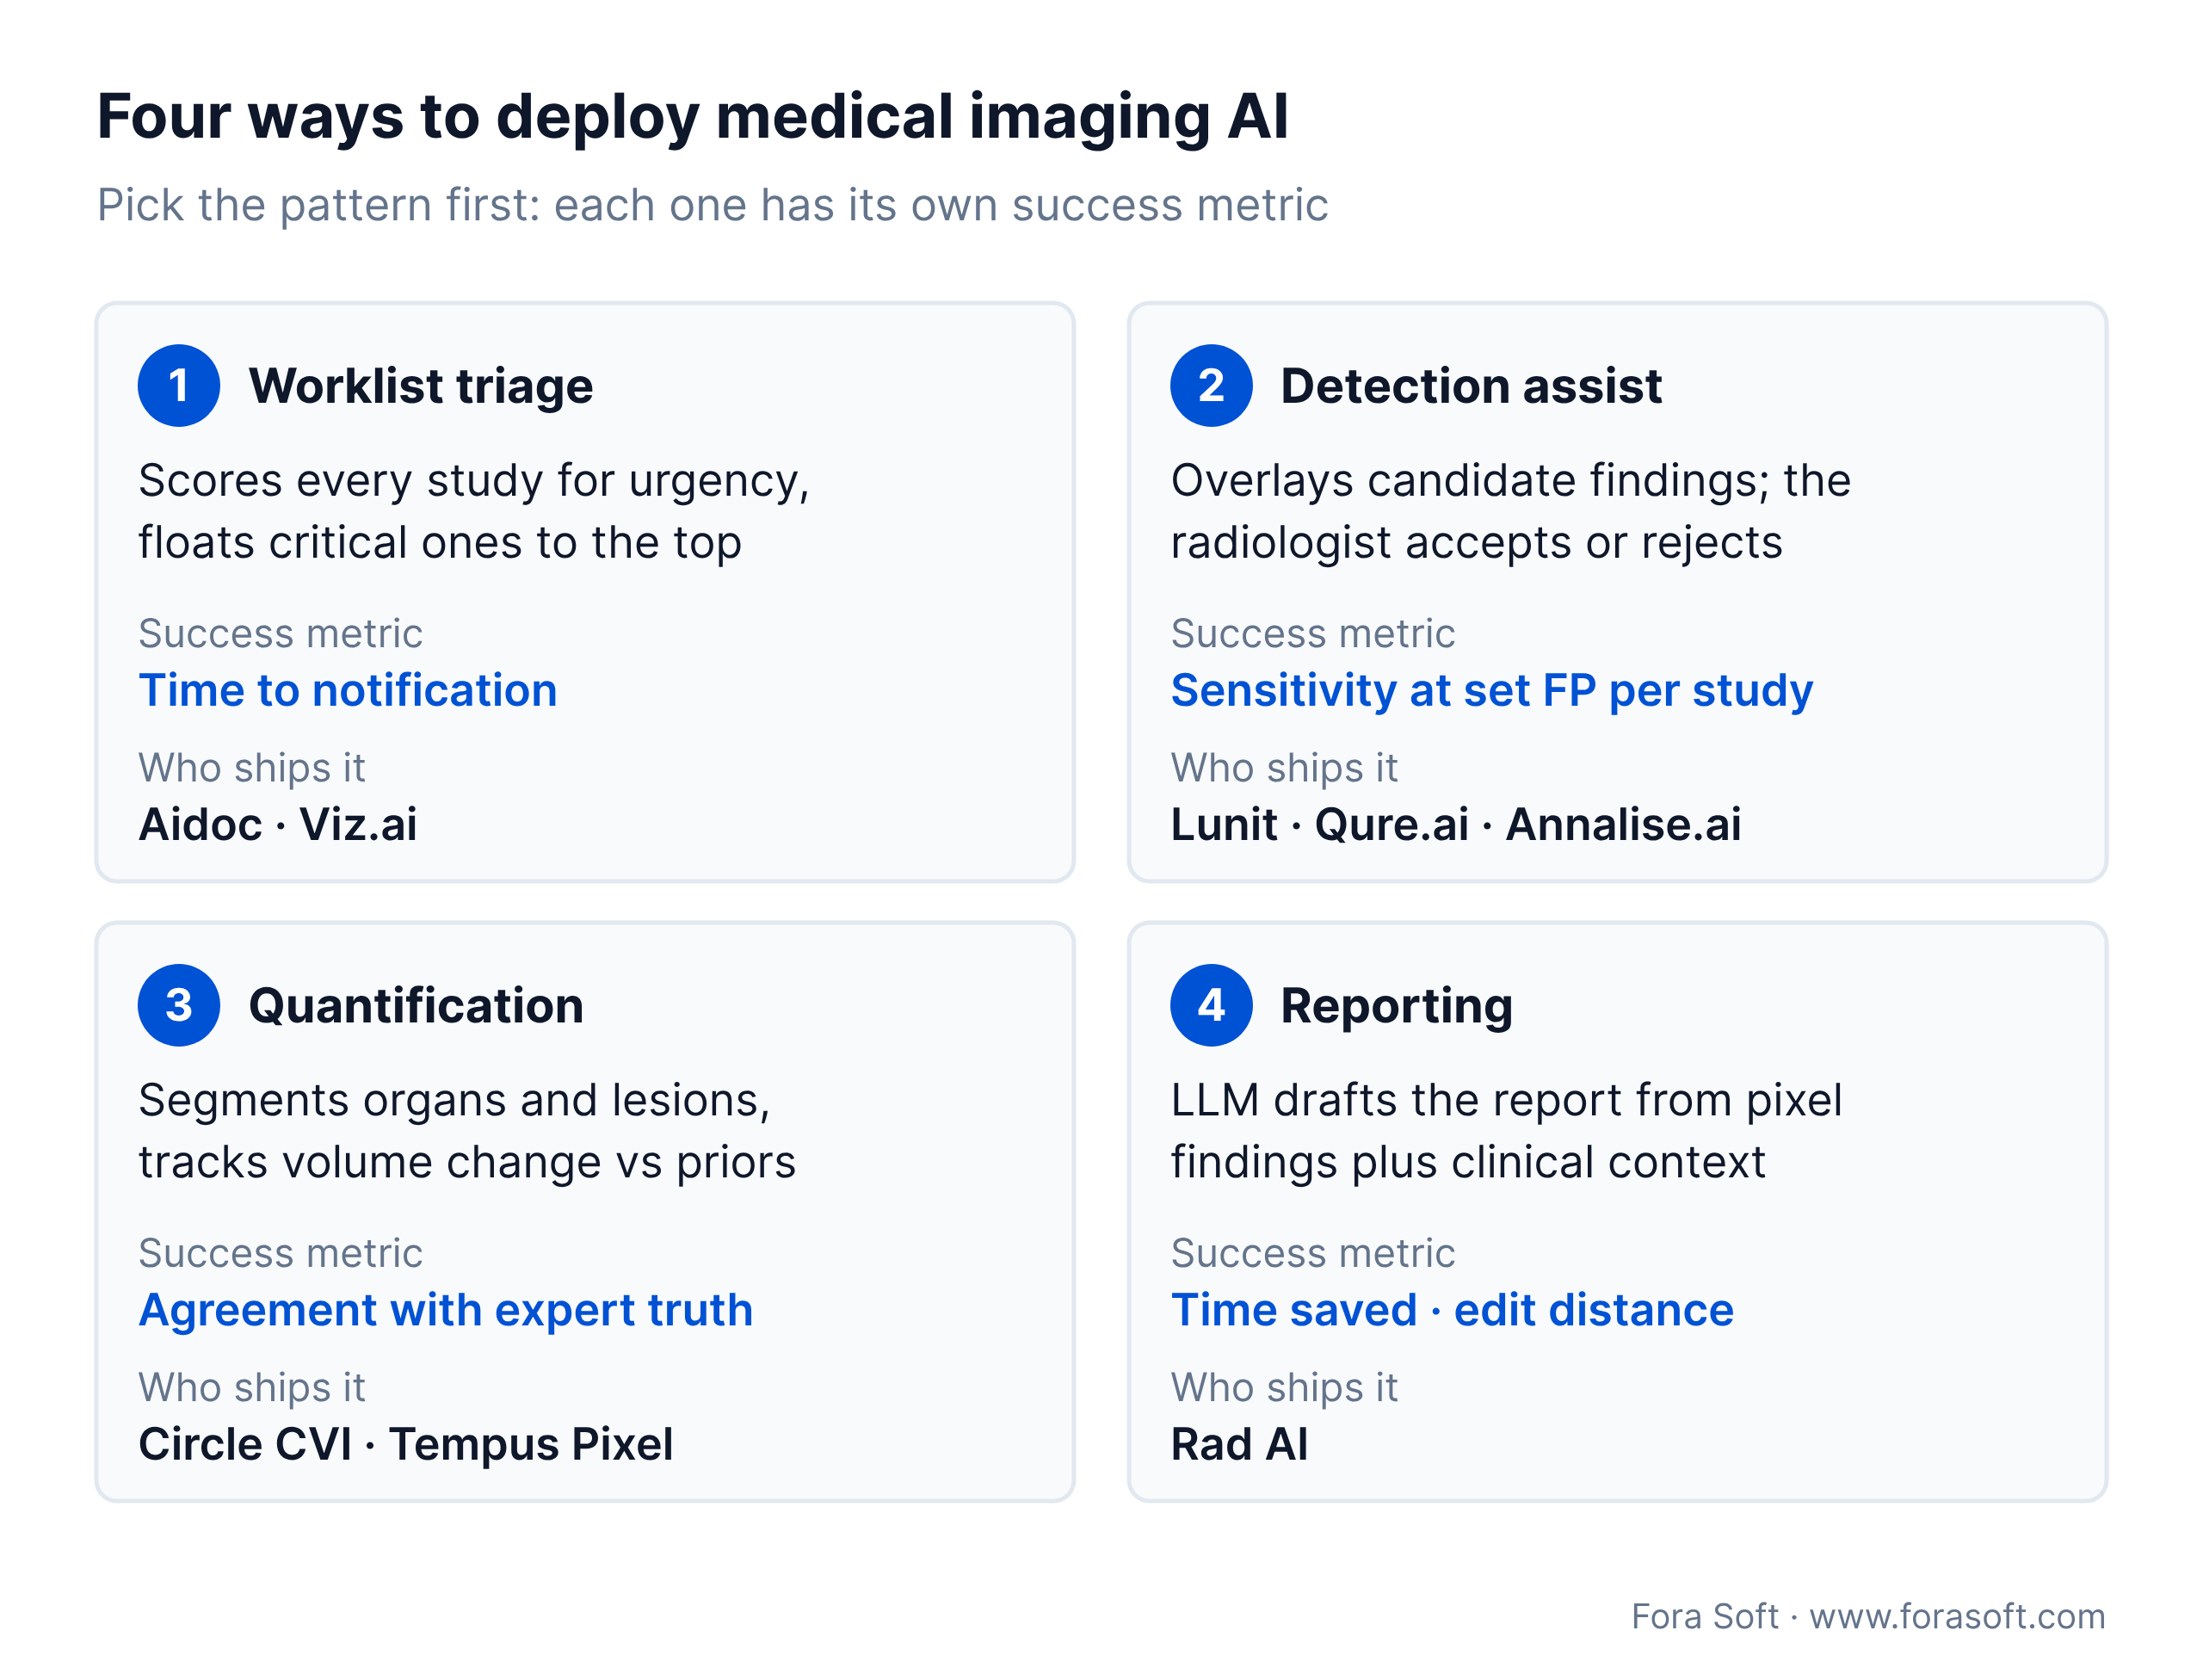
Figure 1. The four deployment patterns. Pick the one that matches your buyer’s workflow before you tune the model.
Market reality for 2026
Global AI in medical imaging is worth $2.57B in 2026 and is projected to reach $22.97B by 2035 (27.6% CAGR), according to the 2026 edition of the Precedence Research report. The FDA’s public AI device list was last updated on September 4, 2026 and now counts 1,614 AI-enabled devices with decisions through June 29, 2026, according to The Medical Futurist’s analysis of that update. A record 335 were authorized in 2025 and 181 in the first half of 2026.
Three facts shape every buying decision. First, radiology dominates the FDA list with 1,230 of the 1,614 devices in the September 2026 update, or 76.2%. Cardiology, pathology, and ophthalmology account for most of the rest. Second, reimbursement now exists. Since January 1, 2026, Category I CPT code 75577 pays for AI quantification of coronary plaque on CCTA, at a national average of $1,021 under the 2026 Medicare Physician Fee Schedule, and CMS has paid NTAP (New Technology Add-on Payments) for AI stroke triage since FY2021. The CY 2027 Physician Fee Schedule final rule, released November 4, 2026, lowers the non-APM conversion factor by 2.31% from January 1, 2027, so check the 2027 rate before you build revenue on that code. Third, hospital procurement is still the slowest step. Sales cycles run 9–18 months, so most successful vendors sell to radiology groups and imaging centers first and use those references to get into hospitals.
AI medical imaging in numbers, as of November 2026:
| Metric | Value | Source and date |
|---|---|---|
| AI in medical imaging market, 2026 | $2.57B; $22.97B by 2035 (27.6% CAGR) | Precedence Research, 2026 edition |
| FDA AI-enabled devices, all specialties | 1,614 (decisions through June 29, 2026) | FDA list, update of September 4, 2026 |
| Share in radiology | 76.2% (1,230 devices) | FDA list, September 2026 |
| Authorized in 2025 | 335, a record year | FDA list, September 2026 |
| Authorized January to June 2026 | 181 | FDA list, September 2026 |
| Medicare payment for AI plaque analysis (CPT 75577) | $1,021 national average | 2026 Medicare PFS |
| Medicare conversion factor, 2027 | −2.31% for non-APM clinicians | CY 2027 PFS final rule, November 4, 2026 |
| EU AI Act high-risk date for medical-device AI | August 2, 2028 | Regulation (EU) 2026/1744 |
| HIPAA Security Rule update | Proposed January 2025; final action projected July 2027 | HHS regulatory agenda, 2026 |
The positions you can win are narrow. “All cancers on CT” has 50 competitors. “Calcium scoring on non-gated CT for incidental screening” has a handful, clean reimbursement, and a clear clinical need. Every cleared device we’ve studied combines a niche specialty, a high-volume study type and a documented workflow problem.
Use cases that actually ship
We place every project on this grid on day one. First question: where does your product sit? Second: who already ships there, and how are you different?
| Modality | Winnable use case | Reference players | Pathway |
|---|---|---|---|
| CT head | ICH / LVO triage, calcium scoring | Aidoc, Viz.ai, RapidAI | FDA 510(k) class II |
| CT chest | Pulmonary embolism, nodule detection, low-dose lung cancer screening | Aidoc, Riverain, Optellum | 510(k) class II |
| CT abdomen | Multi-finding acute triage (14 indications on one model) | Aidoc (CARE foundation model) | 510(k) class II, January 2026 |
| MRI cardiac | LV/RV segmentation, ejection fraction, tissue characterization | Circle CVI, Tempus Pixel (formerly Arterys) | 510(k) class II |
| X-ray chest | Critical-findings triage, TB screening | Annalise.ai, Lunit, Qure.ai | 510(k) + CE mark |
| Mammography | CADe / CADx for breast cancer screening | iCAD (part of RadNet since 2025), Lunit (owns Volpara) | 510(k) + rigorous PCCP |
| Pathology WSI | Prostate, breast, colorectal biomarker scoring | Paige, PathAI, Ibex | FDA De Novo / IVDR |
| Ophthalmology | Diabetic retinopathy screening, OCT glaucoma | IDx-DR (Digital Diagnostics), Eyenuk | FDA De Novo class II |
| Endoscopy | Real-time polyp detection (CADe) | Medtronic GI Genius, Olympus | FDA De Novo + CE mark |
| Operating-room video | Surgical workflow, critical-view-of-safety, event detection | Theator, Activ Surgical, Caresyntax | Workflow analytics can sit outside device rules; clinical alerts from video are a device |
Data strategy: the dataset is the product
The dataset matters more than the model architecture. We’ve seen elegant transformer architectures fail on community-hospital data because the training set came from one academic site with one scanner manufacturer. Our rule of thumb: 3+ geographically distinct sites, 2+ scanner vendors, and explicit demographic balance before you talk about clinical performance.
Public datasets get you to PoC. LIDC-IDRI (lung nodules), NIH ChestX-ray14, MIMIC-CXR, The Cancer Imaging Archive (TCIA), CAMELYON (pathology), RSNA competitions (brain, PE, fracture). Use them for architecture baselines and feasibility demos. Don’t submit a model trained only on public data for FDA clearance: reviewers spot the domain shift right away.
Clinical partnerships get you to MVP. Sign research collaboration agreements with 2–3 hospitals or imaging centers, negotiate Business Associate Agreements under HIPAA, and de-identify DICOM on ingress (strip PHI tags per DICOM Supplement 142). Expect 3–6 months of legal work between first outreach and the first study received.
Federated and synthetic data fill gaps. NVIDIA FLARE and Flower let you train across hospitals without centralizing data, which helps with both compliance and hospital politics. Synthetic augmentation (diffusion models fine-tuned on real scans) helps with rare-finding classes, but FDA examines synthetic data closely.
Annotation is the real cost. Budget $5–$40 per study for radiologist annotation, depending on complexity (a bounding box on X-ray versus pixel-level organ segmentation on 3D MRI). For 10K–30K studies with multi-reader consensus, that comes to roughly $80K to $600K, the biggest line item most teams under-plan. Active learning helps: send the uncertain cases to annotators first. We regularly cut annotation cost by 40–60% this way.
Reference architecture for a cleared imaging AI device
Below is the stack we start from for imaging AI products that have to clear regulators and survive hospital procurement. Every component has open-source and managed alternatives. Our defaults favor proven components that auditors already know.
| Layer | Recommended tech | Why it wins | Alternatives |
|---|---|---|---|
| DICOM ingest | Orthanc + dcm4che | Open-source, IHE-compliant, strong de-identification | Google Cloud Healthcare, AWS HealthImaging |
| ML framework | PyTorch + MONAI + nnU-Net | MONAI is purpose-built for medical imaging (NVIDIA + KCL) | TensorFlow / Keras, JAX |
| Model architectures | nnU-Net (segmentation), TotalSegmentator, SwinUNETR, 3D EfficientNet | Proven baselines; reviewers know them | Custom transformers, foundation models (BiomedCLIP, Google MedGemma and MedSigLIP, 2025) |
| Viewer | OHIF (web) + Cornerstone3D | FDA-grade zero-install viewer, strong annotation API | 3D Slicer, Weasis |
| Inference runtime | NVIDIA Triton + ONNX Runtime | GPU scheduling, batching, version pinning | TorchServe, BentoML, self-hosted FastAPI |
| Orchestration | Kubernetes + Argo Workflows | Reproducible pipelines auditable under 21 CFR Part 11 | Kubeflow, Prefect, Airflow |
| Integration | HL7 v2 + FHIR R4 + DICOMweb (WADO-RS, STOW-RS, QIDO-RS) | Epic / Cerner / Allscripts speak FHIR; PACS speaks DICOMweb | Custom HL7 parsers (avoid unless forced) |
| Hosting | AWS HIPAA-eligible / Azure for Health / GCP Healthcare | BAA coverage, HITRUST-ready | On-prem (edge box in hospital) |
| MLOps | MLflow + DVC + Weights & Biases | Model registry, dataset versioning, experiment tracking — all required for 510(k) submissions | SageMaker, Vertex AI |

Figure 2. A cleared device writes findings back into the existing PACS worklist instead of a separate portal.
FDA, CE mark, and the regulatory choreography
Most imaging AI products in the US end up as Class II medical devices cleared through the FDA 510(k) process. There are three pathways, and picking the right one saves 12+ months.
1. 510(k) with a predicate. You show that your device is substantially equivalent to a predicate that is already cleared. Typical timeline: 9–15 months from PreSub to clearance. Typical engineering, clinical, and filing cost: $150K to $400K on top of product development. Most imaging AI products take this route.
2. De Novo. For a novel intended use with no predicate. IDx-DR (autonomous diabetic retinopathy) went this route. Timeline: 12–24 months, $300K to $800K. It pays off only if you are creating a new category.
3. PMA (class III). For high-risk devices, typically where AI supports life-sustaining decisions. It costs $1M+, takes 2–3 years, and is the wrong pathway for most imaging AI.
Predetermined Change Control Plans (PCCP), set out in FDA’s final guidance of December 2024, let you update a model after clearance without a new 510(k), as long as the changes stay inside a pre-agreed envelope. File a PCCP with your initial submission, or you will re-submit every model update for years. FDA’s January 2025 draft guidance on AI-enabled device software functions lists what reviewers expect in the file: model description, data lineage, subgroup performance, and labeling that tells users how the model was validated.
QMSR since February 2, 2026. FDA’s Quality Management System Regulation replaced the old QSR and incorporates ISO 13485:2016 by reference. A single ISO 13485 QMS now serves both FDA and EU notified bodies, so build it once, starting from the first design-control record.
CDS guidance, January 2026. FDA’s updated clinical decision support guidance widened enforcement discretion for some single-recommendation tools. Software that analyzes a medical image or signal still fails criterion 1 and remains a device, so don’t plan an imaging AI product around the CDS exemption.
EU: MDR + Class IIa/IIb. CE marking under EU MDR is much stricter than it was before 2021. Most imaging AI is Class IIa, some is IIb. Notified-body review takes 6–12 months and costs €100K to €300K. Expect a QMS certified to ISO 13485, risk management to ISO 14971, and clinical evaluation per MDCG 2020-1.
EU AI Act on top of MDR. AI that is a medical device, or a safety component of one, is high-risk under Annex I of the AI Act. The Digital Omnibus on AI (Regulation (EU) 2026/1744, in force since July 27, 2026) moved those obligations from August 2, 2027 to August 2, 2028. Use the extra time to add AI Act data-governance, logging and human-oversight records to your MDR technical file, because the notified body will assess both together.
Other markets. Health Canada Class II, PMDA (Japan), NMPA (China), TGA (Australia), ANVISA (Brazil), SFDA (Saudi Arabia). Most accept 510(k) or CE marking as a reference, but they ask for local clinical data for the commercially important indications.
Reach for a regulatory consultant in week one when: your target market is the US or EU and clinical use is implied. A $30–$60K pre-submission consultation pays for itself 10× in rework you avoid.

Figure 3. Time and cost of the three US clearance pathways. Most AI medical imaging software goes 510(k).
HIPAA, GDPR, and privacy architecture
PHI (Protected Health Information) sits in DICOM metadata, file headers, burned-in annotations, and sometimes in the pixel data itself. The architecture has to handle all four. For the full DICOM de-identification, audit-trail, and compliance architecture, see our medical imaging software development playbook and our telemedicine engineering notes.
1. De-identification at ingest. Apply the DICOM Supplement 142 / PS3.15 confidentiality profile, strip burned-in overlays, run OCR on annotated pixels to catch accidental PHI, and log every redaction for audit.
2. BAA coverage everywhere. AWS, Azure and GCP all offer HIPAA-eligible services under a signed BAA, but the BAA covers only specific services. Check each one. Sub-processors (Weights & Biases, MLflow Cloud, Segment) also need BAAs or have to stay out of PHI paths.
3. Encryption and access. AES-256 at rest, TLS 1.3 in transit, IAM with least-privilege roles, audit logs in immutable storage (S3 Object Lock), and 6-year retention of access logs for HIPAA. HHS’s January 2025 proposed Security Rule update would make encryption and MFA mandatory instead of “addressable”. The federal regulatory agenda now projects final action for July 2027, so design for it now.
4. GDPR and EU data residency. Imaging data is an Article 9 special category, so you need explicit consent or a statutory basis. Stay in EU regions, document DPIAs, and build right-to-erasure workflows that purge data from backups within statutory deadlines.
5. HITRUST and SOC 2 Type II. Any US hospital over 250 beds will expect them. HITRUST i1 takes 6–9 months and $60K to $150K; SOC 2 Type II takes 6 months and $25K to $60K. Run them in parallel, since much of the work overlaps.
Workflow integration — the feature that decides adoption
KLAS Research and several peer-reviewed surveys name workflow friction as the #1 reason imaging AI never reaches routine use. If a cleared device adds three clicks to the radiologist’s workflow, nobody will use it.
PACS-side integration. Listen on DICOM DIMSE (C-STORE, C-FIND) or DICOMweb (STOW-RS). Send findings back as DICOM SR (Structured Report) or as secondary-capture PDFs. The rule: findings show up in the radiologist’s existing worklist, never in a separate vendor portal.
EHR-side integration. The gateways are the developer programs of Epic Vendor Services (the successor to App Orchard) and Oracle Health (formerly Cerner). Use FHIR R4 for contextual launch (SMART on FHIR) and HL7 v2 ADT and ORU feeds for enrollment and result delivery. Budget 6–12 weeks per major EHR for production-grade integration.
Reading-room UX. Show findings directly in the existing viewer (Sectra, Visage, McKesson, Mach7) through vendor-neutral plugin frameworks; OHIF and Sectra IDS7 have APIs. Support hanging protocols, respect window/level presets, and never auto-scroll.
Orchestration vendors as distribution. Microsoft Precision Imaging Network (formerly Nuance), Sectra Amplifier Marketplace, CARPL.ai, and deepc put your device one click away from hospitals that already use their PACS or reporting stack. Revenue share is typically 15–30%, and for most startups the distribution is worth it. Keep a direct DICOMweb path as a fallback: Bayer shut down its Calantic platform in September 2025 and sold Blackford to Sopris Capital in October 2026, and customers on those channels had to re-plan their integrations.
Reach for an AI orchestration marketplace when: you’re pre-Series B and can’t staff 20 enterprise-integration engineers. Let a marketplace such as Microsoft Precision Imaging Network or Sectra Amplifier handle the PACS plumbing while you work on the model and the FDA submission.
Performance metrics that stand up to clinical scrutiny
“95% accuracy” is a marketing number. FDA reviewers and hospital radiologists look at task-specific metrics on properly stratified test sets.
| Task | Primary metric | Useful threshold | What reviewers also want |
|---|---|---|---|
| Classification (triage) | AUC-ROC, sensitivity at fixed specificity | AUC ≥ 0.92, sens ≥ 0.90 at spec 0.85 | Subgroup performance by site, vendor, demographics |
| Detection | Sensitivity at false-positive rate per study | ≥ 0.85 sens at ≤ 1.0 FP/study | FROC curves, per-lesion-size stratification |
| Segmentation | Dice / IoU vs expert ground truth | Dice ≥ 0.85 for major organs | Hausdorff distance, per-slice consistency |
| Quantification | Bland-Altman, ICC vs expert | ICC ≥ 0.90, LoA clinically acceptable | Test-retest reliability across reconstructions |
| Report drafting | Radiologist edit distance, time saved | < 15% edit rate, > 30% time saved | Blinded reader study comparing drafted vs de novo reports |
Two habits separate shipped products from models that stay in research: (1) calibration with Platt scaling or isotonic regression, so reported probabilities match observed frequencies, and (2) subgroup analysis by race, sex, age, scanner vendor, slice thickness, and contrast protocol. FDA reviewers now flag models that perform 10+ points worse on any identifiable subgroup.
Need a regulatory-aware build plan and realistic timeline?
Share your use case, modality, and target market. We’ll return a 12–20 week PoC plan plus a clearance-aware production roadmap within 5 business days.
Realistic cost model (with Agent Engineering)
These numbers reflect Fora Soft delivery. Traditional agencies typically quote 25–50% higher for the same scope, so compare quotes by scope, not by hours. If the scope itself is still open, our MVP planning sprint turns the use case, competitor set and feature priorities into a launch blueprint in 3 business days, before anyone writes model code.
| Stage | Timeline | Scope | Budget |
|---|---|---|---|
| PoC / feasibility | 6–10 weeks | Public-data baseline, model on representative cohort, performance report | $30K–$80K |
| Production MVP | 4–7 months | PACS integration, OHIF viewer, inference service, HIPAA posture, multi-site validation | $120K–$260K |
| Cleared class-II device | 12–20 months | Above + 510(k) filing, QMS, clinical validation study, PCCP, CE mark | $320K–$750K |
| Annotation | Parallel | 10K–30K studies, multi-reader consensus | $80K–$600K |
| Year-2 opex | Continuous | GPU infra, monitoring, drift detection, 3–5 FTE, compliance refresh | $220K–$650K/year |
Infrastructure for a 50-hospital deployment costs around $8K to $25K/month: GPU inference (A10 / L4 / H100 depending on the model), HIPAA-tier storage, monitoring, and DICOM router replicas in each region. Plan for 99.95% uptime with active-active across 2+ regions. A missed ICH triage during downtime can harm a patient, which is worse than any SLA breach.

Figure 4. What a custom AI medical imaging software build costs, stage by stage, with Agent Engineering.
Mini case: from PoC to pilot in 14 weeks
Situation. Before raising a Series A, a US imaging startup wanted to prove that its CT-chest triage model could run inside real hospital PACS and on more than research data. It had four months of runway, no regulatory staff, one radiologist co-founder, and a prototype trained only on public datasets that looked good on paper.
12–14 week plan. We ran specialist agents in parallel. The data team negotiated two imaging-center partnerships and built the de-identification pipeline. The ML team ported the baseline to nnU-Net + MONAI with 3-fold cross validation on the new data. The integration team set up Orthanc + OHIF and a Blackford orchestrator channel. The compliance team documented design controls against IEC 62304 and ISO 14971 while the code was being written.
Outcome. By the end of week 14 the startup had a pilot running at one imaging center with 40–80 studies/day, performance within 2 points AUC of the predicate, a PreSub package ready for FDA, and a story investors could fund. The founder closed a $6M seed round on the pilot data. That pace (PoC in 10 weeks, pilot in 14) is what Agent Engineering gives you compared with the 8–12 month traditional timeline.
MLOps and post-market surveillance
Shipping the model is only the start. FDA’s “Good Machine Learning Practice” guidance and EU MDR both require ongoing performance monitoring and a documented response to drift. Four practices keep the device working after launch.
1. Drift monitoring. Log input-distribution statistics (scanner vendor mix, slice thickness, contrast, demographics) and flag shifts >2 standard deviations. Track the output distribution as well: a sudden rise in the positive rate usually points to an input change, not a real change in prevalence.
2. Shadow-mode evaluation. Before a model update goes live, run it in shadow mode on production traffic for 2–4 weeks and compare its agreement with the current model. Any discrepancy >5% goes to clinical review.
3. Ground-truth feedback. Record radiologist agreement or disagreement at the workstation. Report monthly to the quality team and review quarterly with the medical director. The same data feeds retraining under your PCCP.
4. Adverse-event reporting. MDR (Medical Device Reporting) under 21 CFR 803 requires you to report device malfunctions that could cause serious harm within 30 days. Set up the internal process before you need it.
Build vs buy vs embed
Three paths, different math.
| Path | When to choose | Year-1 cost | Trade-off |
|---|---|---|---|
| Build custom | Novel use case, proprietary data, regulatory moat | $320K–$750K + annotation | Full IP ownership; 12–20 month clearance path |
| License cleared model | Use case already covered, fast go-to-market | $100K–$400K licensing + integration | No IP, narrow customization, per-study fees forever |
| Embed via marketplace | Distribution-first, focus engineering on model only | 15–30% rev share | Fast scale, thinner margins, marketplace controls UX |
| Open-source stack (MONAI, nnU-Net) | Research, internal tooling, non-commercial | $30K–$120K engineering | Cannot be sold as medical device without clearance |
Reach for custom build when: your edge is the data or the indication (e.g., rare disease, unique modality, unusual clinical workflow). A licensed model will trail your specific use case by 12+ months.
Decision framework — five questions to choose your path
1. Is the intended use already cleared by anyone? If yes, and your model is not clearly better or differently positioned, license or partner. If no, a custom build is defensible and your regulatory story is clearer.
2. Do you have dataset access or a path to it? That means 3+ sites, 2+ scanner vendors, a documented annotation protocol, and signed BAAs. If you don’t, spend the first 8 weeks on data partnerships before writing code.
3. Who is the economic buyer and what do they reimburse? Radiology group, imaging center, hospital IT, or MedTech OEM. Existing reimbursement (NTAP, CPT) helps a lot. Without it, sales are hard.
4. What’s the realistic runway? 12 months funds PoC + MVP; 24 months funds MVP + 510(k); 36 months funds clearance + pilot revenue. Scope the build to fit.
5. Who owns clinical validation? A named radiologist co-founder or a strong clinical advisory board shortens every timeline. Without clinical authority, add +6 months for building trust.
Pitfalls we see kill imaging AI projects
1. Public-data-only training. Great PoC numbers fall apart on community-hospital data. Line up 2–3 partner sites before month three.
2. Ignoring the workflow. A 0.95 AUC model in a separate browser tab gets used 4% of the time. Integrate with the existing PACS worklist and viewer instead of running next to them.
3. Skipping the PreSub. FDA Q-Subs are free and quick, with a 60–90 day turnaround. Skip one and you learn the predicate and clinical-study expectations from an Additional Information Request, after 180 days of delay.
4. Under-budgeting annotation. “10K studies” in a plan usually costs 10x more than the plan assumes. Budget for active-learning pipelines and consensus protocols from day one.
5. One-scanner bias. A model trained on GE studies fails on Siemens reconstructions. Stratify training and test sets by scanner vendor, slice thickness, and contrast protocol, and report subgroup performance in every submission.
KPIs to monitor from pilot onward
Clinical KPIs. Sensitivity and specificity within the pre-specified CI at every site, checked quarterly; time-to-notification for urgent findings (< 5 minutes from image arrival to PACS alert); radiologist agreement rate > 85% on post-hoc review.
Engineering KPIs. Inference latency p99 < 60 seconds for CT, < 10 seconds for X-ray; pipeline success rate > 99.5%; drift alerts triaged within 24 hours.
Business KPIs. Studies processed per month per customer (the activation metric), radiologist acceptance rate on AI findings, average time saved per study, and NRR > 110% after year one.
When NOT to build custom medical imaging AI
We take three signals seriously. First, if your only data source is one hospital with one scanner, the model will not generalize and will not clear FDA. Build partnerships first and write code later.
Second, if clinician-buyers can’t say why they should care compared with the three cleared products already in the space, the commercial case fails before the FDA case does. Change the use case.
Third, if the runway covers only a PoC but the goal is a fully cleared device, scale the plan to the runway: ship the PoC, validate it with one partner site, and raise a Series A on the evidence. Most imaging-AI startups that failed tried to skip this step.
Unsure if your idea clears — or should license?
30 minutes with our ML and regulatory architects. We’ll tell you which path fits your use case, dataset, and runway — and walk through the PreSub strategy.
A 14-week PoC-to-pilot delivery roadmap
This is how we run a medical imaging AI PoC-to-pilot under Agent Engineering, with data, ML, integration, compliance, and QA agents working in parallel. Traditional teams typically need 20–24 weeks for the same scope.
| Weeks | Milestone | Deliverables |
|---|---|---|
| 1–3 | Discovery + data partnerships | Use case lock, predicate review, BAAs with 2 sites, de-identification spec |
| 2–6 | Baseline model + annotation pipeline | nnU-Net baseline on public data, annotation UI, active learning loop |
| 4–8 | PACS integration + viewer | Orthanc DICOM router, OHIF viewer, DICOM SR output, orchestration-marketplace channel |
| 6–10 | Multi-site training + validation | Cross-site training, subgroup analysis, calibration, reader study |
| 8–12 | Compliance + QMS | ISO 13485 QMS, IEC 62304 software-of-unknown-provenance plan, risk file |
| 10–13 | Pilot deployment | Live at 1 partner site, QoS monitoring, radiologist feedback capture |
| 12–14 | PreSub package | FDA Q-Sub meeting request, draft 510(k) outline, PCCP |
Reach for Agent Engineering when: you want PoC-to-pilot in 14 weeks instead of 24, with specialist agents on data, ML, PACS, compliance, and QA working in parallel rather than in sequential sprints.
FAQ
How long and how expensive is FDA 510(k) for a medical imaging AI?
A typical 510(k) with a predicate takes 9–15 months from PreSub to clearance and costs $150K to $400K on top of engineering (QMS, testing, clinical validation, filing). De Novo (no predicate) takes 12–24 months and $300K to $800K. File a Predetermined Change Control Plan with your initial 510(k) so that post-clearance model updates don’t each need a new filing.
What dataset size do we need for clinical-grade performance?
It depends on the task and prevalence. Triage of common findings (PE, ICH): 8K–20K studies from 3+ sites. Rare findings (unusual fractures, uncommon tumors): 30K–100K with synthetic augmentation. Segmentation models need fewer subjects but much richer annotation (pixel-level, 3D). Budget $5–$40 per study for annotation, depending on complexity.
Do we need Epic or Cerner integration to sell to US hospitals?
For enterprise deals, eventually yes. An orchestration marketplace (Microsoft Precision Imaging Network, Sectra Amplifier, CARPL.ai, deepc) gets you PACS-level integration in weeks, while a direct Epic integration through Epic Vendor Services takes 6–12 months. Start with orchestrators and add direct EHR integration when a $500K+ contract justifies it.
Can we start with a research prototype and productize later?
Yes, and most teams take this path. Getting from research prototype to cleared product typically takes 9–15 months and $400K to $900K (HIPAA hosting, PACS integration, clinical validation, QMS, filing). The quality of the research code is a strong predictor of that timeline. Using MONAI + MLflow + DVC from week one cuts later refactoring in half.
Do we need HIPAA BAAs with every sub-processor?
Yes, if PHI ever passes through the sub-processor. AWS, Azure and GCP offer BAAs that cover specific HIPAA-eligible services, not all of them. Observability (Datadog), experiment tracking (W&B), email (SendGrid) and analytics (Segment / Amplitude) all need BAAs or have to stay out of PHI paths. Audit every data flow at design time.
What’s the right metric to report to hospital customers?
Use task-specific metrics: sensitivity at a fixed specificity for triage, sensitivity at a false-positive rate per study for detection, Dice / Bland-Altman for segmentation and quantification. Always include subgroup performance (scanner vendor, slice thickness, demographics), because hospitals and FDA both ask for it. Skip raw “accuracy”, which is a marketing metric.
Can we use foundation models (BiomedCLIP, MedGemma) in a cleared device?
Yes, but expect extra scrutiny. FDA wants full traceability of training data and stable model behavior. For a foundation-model fine-tune, document the base model’s training data as far as it is disclosed, freeze the base, and validate the fine-tuned task exactly like any custom model. The first clearances exist: in January 2026 Aidoc received a 510(k) for abdomen CT triage built on its CARE foundation model, covering 14 indications, 11 of them new. Purpose-built architectures (nnU-Net, SwinUNETR, 3D EfficientNet) still have the most familiar regulatory story.
What is AI medical imaging software?
AI medical imaging software is a program that reads DICOM studies (CT, MRI, X-ray, ultrasound, pathology slides) and returns a triage score, a detection overlay, a measurement, or a draft report inside the radiologist’s PACS. Once it informs diagnosis, it is regulated as a medical device. In the US most products are Class II and cleared through 510(k).
How is AI medical imaging software different from radiology software?
Radiology software, also called diagnostic imaging software, is the system radiologists already work in: PACS to store and view studies, RIS to schedule and track them, and the reporting tool. AI medical imaging software plugs into that stack. It reads the same DICOM studies and writes its triage score, overlay or measurement back into the PACS worklist and viewer. Advanced imaging software, such as 3D post-processing, sits between the two.
Which FDA-cleared AI radiology software leads in 2026?
By category: Aidoc, Viz.ai and RapidAI in CT triage (stroke, hemorrhage, PE); Lunit, Annalise.ai and Qure.ai in chest X-ray; iCAD and Lunit in mammography; Paige and PathAI in pathology; Rad AI in report drafting. Radiology holds 76.2% (1,230) of the 1,614 AI-enabled devices on FDA’s September 2026 list, so most categories already have several cleared products.
How much do AI diagnostic support tools cost a hospital system?
Hospitals usually pay for a licensed tool per study, per scanner, or through an annual enterprise subscription, plus integration and an IT security review. Prices are rarely public and depend on volume and the number of algorithms. Building your own cleared product costs $320K to $750K plus annotation (see the cost model above).
What should a scalable AI radiology platform for multi-site clinics have?
It needs vendor-neutral DICOMweb ingest from every site’s PACS, results written back as DICOM SR into the existing worklist, performance monitoring per site and per scanner, a PCCP for model updates, and a signed BAA for every service that touches PHI. Ask vendors for subgroup performance by site and scanner vendor rather than one headline AUC.
Edge or cloud for real-time imaging AI across several hospitals?
Run inference where latency and data residency require it. Put an edge GPU node inside each hospital for urgent triage (stroke, hemorrhage) and for sites that don’t let PHI leave the network. Use a HIPAA-eligible cloud region for batch reads, monitoring and retraining. Connect the two over a VPN or private link with TLS 1.3, and send only de-identified data to the cloud whenever the use case allows.
How does Fora Soft’s experience apply to medical imaging specifically?
We’ve built video and AI software since 2005, so deep learning on video is routine for us, and imaging AI needs exactly that. We have also shipped HIPAA, BAA and SOC 2 compliance work across BrainCert, our telemedicine platforms, and the dedicated AI medical imaging practice. Agent Engineering shortens the traditional 20-24 week pilot to 12–14 weeks without skipping validation.
What to Read Next
Real-time AI
Real-Time AI on Video: Architecture Patterns
How we push CNNs through live video at clinical latency — directly relevant to endoscopy and OR video analysis.
AI + video
AI Video Quality Enhancement: The Real Stack
Super-resolution and denoising patterns that map cleanly onto low-dose CT and MRI acceleration.
ML systems
Recommendation Systems: Architectures Compared
Two-tower architectures, calibration, and subgroup analysis — same tooling we use to validate imaging classifiers.
AI engineering
AI Video Streaming App Development Guide
The AI-plus-video engineering patterns that transfer directly to telemedicine and imaging AI products.
Ready to ship a medical imaging AI that clinicians actually use?
AI medical imaging software succeeds when the model is good enough, the regulatory strategy is clear, and the product lives inside the radiologist’s existing workflow. Pick a narrow use case with clean reimbursement, build a dataset from 3+ real sites, set up MLOps for drift and subgroup monitoring, and integrate through PACS and orchestration marketplaces before you worry about Epic.
If you’re scoping a build, we have run our 14-week PoC-to-pilot plan on real projects. If you need a regulatory sanity check or an honest build-vs-license call, we’ll give you that too, in 30 minutes and without a sales deck.

The book · Volume 6 of 7
AI for Video: A Complete Guide to Intelligence in Video Products: From Models and Inference to Computer Vision, Speech, Search, and Generative Video
Clearance and PACS workflow decide whether imaging AI ships; the model work underneath decides whether it is worth clearing. Volume 6 of our handbook covers the AI feature lifecycle, segmentation and detection models, deployment topologies and model artifacts, and the ML basics behind build, buy or embed calls, so the team can plan a PoC that survives clinical review. Written by Nikolay Sapunov, CEO at Fora Soft.
Read it on Amazon →Kindle & paperback · Fora Soft Video Engineering Handbook
Let’s scope your medical imaging AI together
30 minutes with our ML, regulatory, and integration architects. We’ll sketch use case, dataset path, and a clearance-aware roadmap tailored to your runway.

